Monitoring the Workforce Outcomes of North Carolina Medical School Graduates: Retention In State and in High Need Geographic Areas and Specialties
By Evan Galloway, Erin Fraher, Nathan Tarr, Catherine Moore, Hugh H. Tilson Jr.
Aug 14, 2026
Executive Summary
In 1993, the General Assembly required the University of North Carolina’s Board of Governors to submit an annual report to the legislature on the number of North Carolina (NC) medical school graduates going into primary care. Since 1994, the Cecil G. Sheps Center for Health Services Research at the University of North Carolina at Chapel Hill (“Sheps Center”) and the NC Area Health Education Centers program (AHEC) have collaborated to produce this report which tracks the number of students practicing primary care in rural NC five years after graduation from an NC medical school. As a result of the legislative mandate, NC is a national model for tracking medical student outcomes.
As in prior years, this report summarizes the Sheps Center’s analysis of the workforce outcomes for physicians who graduate from the state’s five medical schools, including whether they practice in North Carolina, in rural areas, in high-need specialties, and in NC safety net settings1 five years after graduation. Appendix B details data collected by the NC AHEC on each medical school’s efforts to increase the number of graduates practicing primary care in rural NC. Appendix C reports on AHEC’s on-going efforts to establish a “Pathway to Primary Care” in NC.
Historically, this report examined NC medical school outcomes five years after graduation, per the legislative mandate. However, this period is not ideal because the time required to complete residency after medical school graduation ranges from three to more than six years for different physician specialties. At five-years post-graduation from medical school, physicians in psychiatry, obstetrics & gynecology (ob-gyn), surgery, and medicine/pediatrics are just completing residency, or may be in fellowship/specialty training, and may not have settled in a permanent practice location. Thus, although not required by the legislature, this report also includes ten-year outcomes for the 2015 cohort. The Campbell School of Osteopathic Medicine graduated its first class in 2017, so they are included in the outcomes measured at 5 years but not 10 years.
Analyses of the five-year outcomes of NC class of 2020 graduates and ten-year outcomes of NC class of 2015 graduates show:
- Of the 614 NC medical school graduates from the class of 2020, 201 (33%) were retained in NC, 69 (11%) were in practice or training in primary care in NC, and 10 (2%) were in primary care in a rural NC county in 2025, five years after graduation.
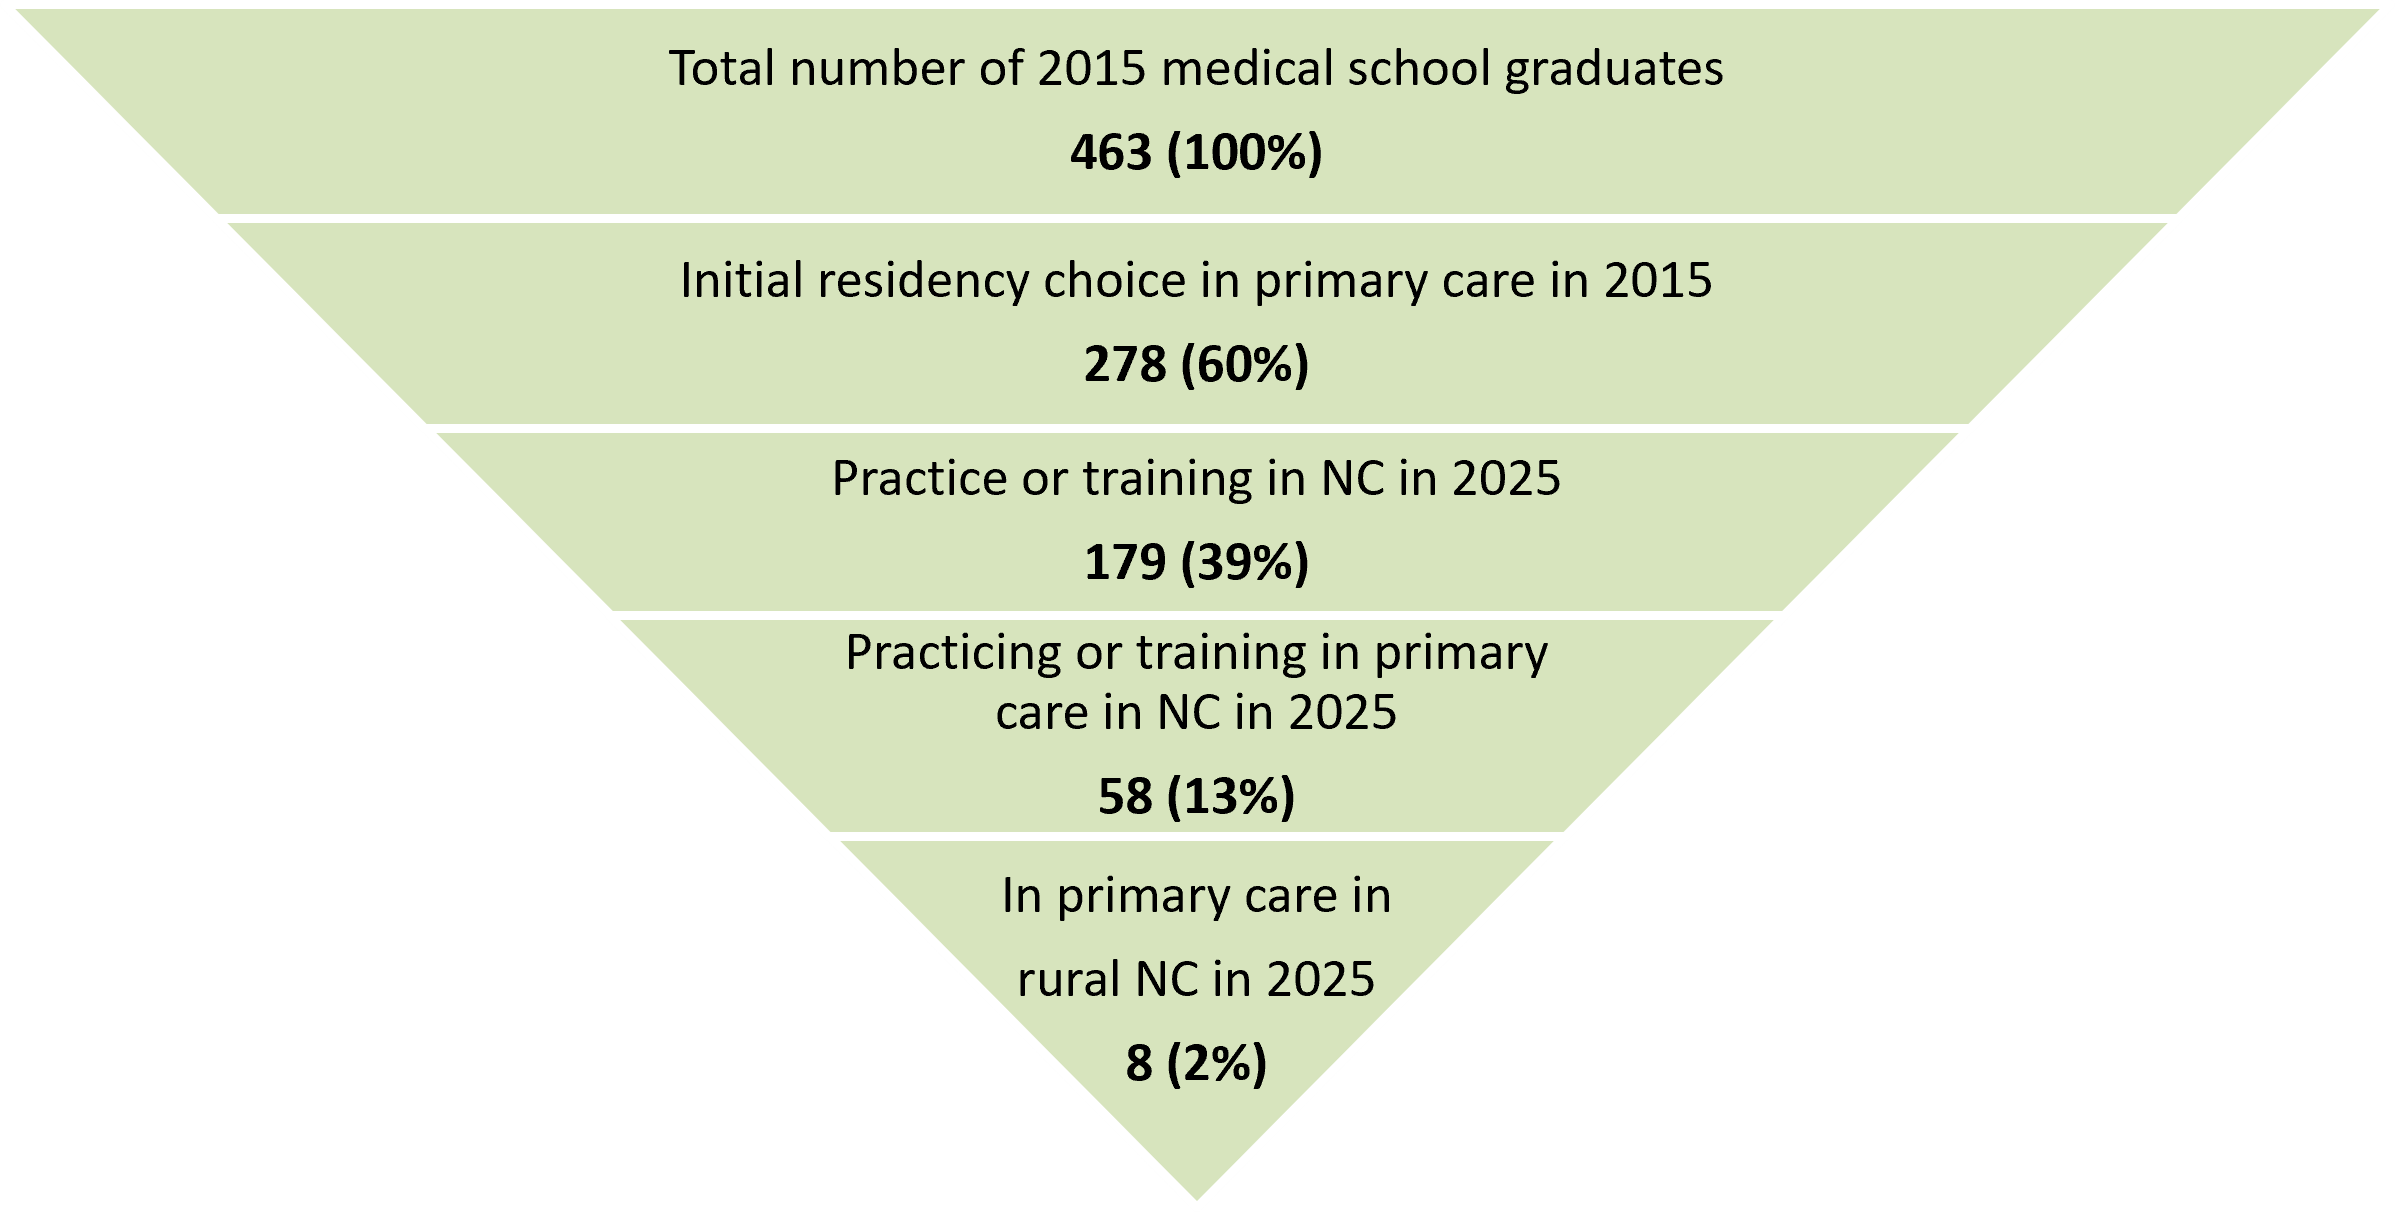
- Of the 463 NC medical school graduates from the class of 2015, 179 (39%) were retained in NC, 58 (13%) were practicing primary care in NC and 8 graduates (2%) were in rural primary care in NC in 2025, ten years after graduation.
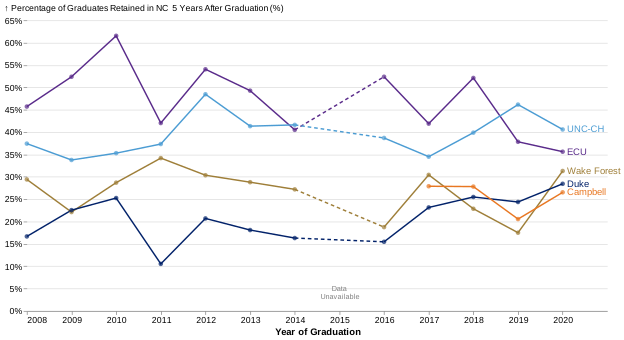
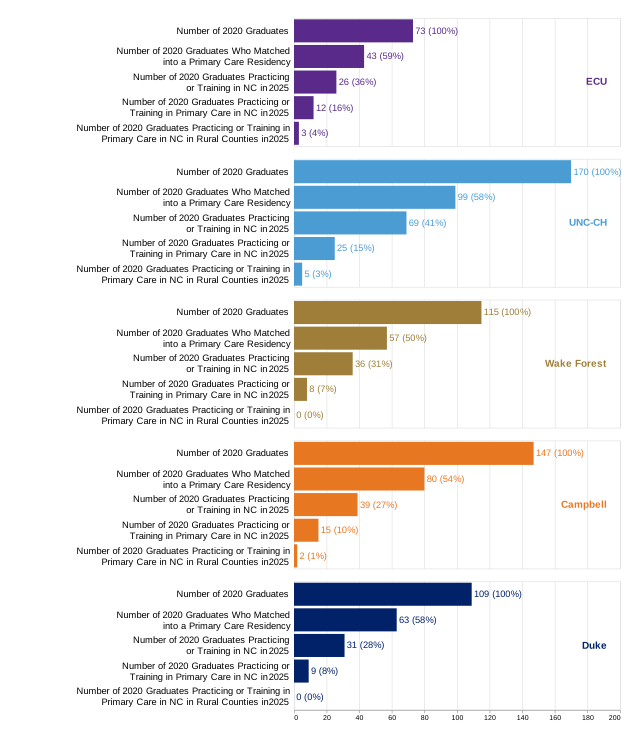
- UNC-CH and ECU retained the largest proportion of 2020 graduates in practice or training in NC in any specialty after five years (41% and 36%, respectively), followed by Wake Forest (31%), Duke (28%), and Campbell University (27%).
- ECU and UNC-CH had the largest proportions of 2020 graduates practicing in primary care in NC five years after graduating (16% and 15%, respectively). From this cohort, UNC-CH contributed 25 graduates to the state’s primary care workforce, followed by Campbell with 15 and ECU with 12.
- Across both the 2020 and 2015 cohorts, 10 graduates were practicing or training in safety net settings (5 from each cohort) that deliver care to uninsured, Medicaid, and other vulnerable populations five and ten years, respectively, after graduation.
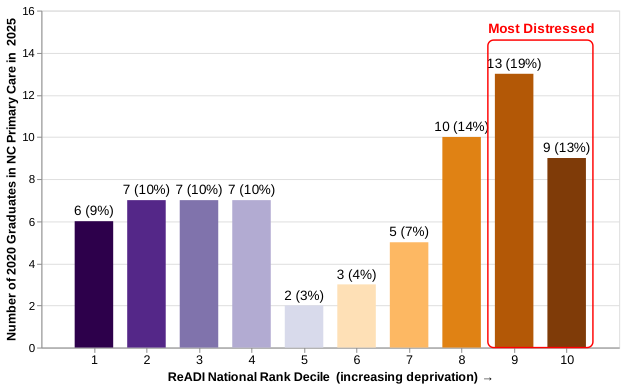
- Among graduates practicing primary care in NC, 32% of the class of 2020 (22/69) and 16% of the class of 2015 (9/58) worked in a practice location in the most economically distressed areas of NC five and ten years, respectively, after graduation.
- Four 2015 graduates were in practice in general surgery in NC ten years after graduating, but none had a primary practice in a rural county. Ten graduates from the same year were practicing psychiatry in NC ten years later, with none practicing primarily in a rural county.
It is important to consider this report’s finding that relatively few NC medical students end up in primary care specialties and rural areas in the context of broader workforce trends in the US. National data show a declining proportion of medical school graduates and residents entering primary care careers.2 Also important for contextualizing the findings is the fact that a physician’s training pathway is long; medical school is just one component of a physician’s training that shapes their career trajectory.
Where a physician completes residency training is a better predictor of where they will end up in practice than medical school location.3,4 Physicians who complete residency training in rural areas and community-based settings are more likely to choose rural, primary care careers.5 The number of graduates of North Carolina residency programs increased from 1,145 in 2017 to 1,264 in 2019. On average, just 37% of these graduates were retained in active practice in NC five years after graduation and 3% were in rural communities.6 However, nearly 65% of “double” NC educated/trained physicians were retained in-state after five years, underscoring the return on investment of building in-state pathways from medical school to residency training.
Background
In 1993, the North Carolina General Assembly expressed a desire to expand the pool of generalist physicians (i.e., primary care physicians) for the state. To increase the supply, the General Assembly passed legislation (N.C.S.L.1993-321.) that required each of the state’s four medical schools to develop a plan to expand the percent of medical school graduates entering “residencies and careers in primary care.” Primary care was defined as family practice, general internal medicine, general pediatric medicine, internal medicine-pediatrics, and obstetrics & gynecology. It set the goal for 60% of East Carolina University (ECU) and UNC Schools of Medicine graduates to enter primary care; for the Wake Forest University and Duke University Schools of Medicine, it set the goal at 50%. Campbell University School of Osteopathic Medicine graduated its first class in 2017 and was therefore not included in these original goals.
Since 1994, the Cecil G. Sheps Center for Health Services Research at the University of North Carolina at Chapel Hill (“Sheps Center”) and the NC Area Health Education Centers program (AHEC) have collaborated to produce this report tracking the workforce outcomes for NC medical schools. As a result of the legislative mandate, NC is a national model for tracking medical student outcomes. Data from this report were featured in the New England Journal of Medicine as an example of how to track workforce outcomes by Iglehart (2018) in “The Challenging Quest to Improve Rural Health Care.”7
While not required by the original legislation, the Sheps Center and NC AHEC have enhanced the annual report to better reflect the state’s workforce needs. As in prior years, this report tracks NC medical school graduate outcomes for physicians who practice in NC and in rural NC counties. However, this report also includes an analysis of the number of medical school graduates that practice in NC safety net settings that deliver care to uninsured, Medicaid, and other vulnerable populations and in areas of high economic deprivation in NC. In addition to tracking graduates entering primary care, we also include an analysis of graduates retained in other high need specialties in NC including psychiatry and general surgery.
Also not required by the legislation is tracking medical school graduates beyond five years. The five-year period specified in (N.C.S.L.1993-321.) is not ideal for assessing practice behaviors because the time required to complete residency after medical school graduation ranges from three to more than six years for different physician specialties. At five-years post-graduation from medical school, physicians in psychiatry, obstetrics & gynecology (ob-gyn), surgery, and medicine/pediatrics are just completing residency, or may be in fellowship/specialty training, and may not have settled in a permanent practice location. This is typically the case for general surgeons, whose training period is five years, and for ob-gyns, psychiatrists and medicine/pediatrics residents who often do a fellowship after a four-year residency. At ten years following graduation from medical school allows for physicians to complete fellowship training following residency. Thus, this report also includes ten-year outcomes for the 2015 cohort.
Since reporting on medical student outcomes began in 1994, Campbell University became the fifth medical school in North Carolina and is now included in this report. As other new medical schools open in the state, their workforce outcomes will also be tracked in this report.
Findings
Class of 2020 Five-Year Outcomes
Figure 1 shows the outcomes of the class of 2020, five years after graduation. Out of the 614 medical school graduates in 2020, 201 (33%) were in practice or training in NC in 2025 and 69 (11%) were in training or practice in primary care in NC in 2025 (Figure 1).
Figure 1. Retention of 2020 NC Medical Graduates in NC Rural Primary Care Five Years After Graduating
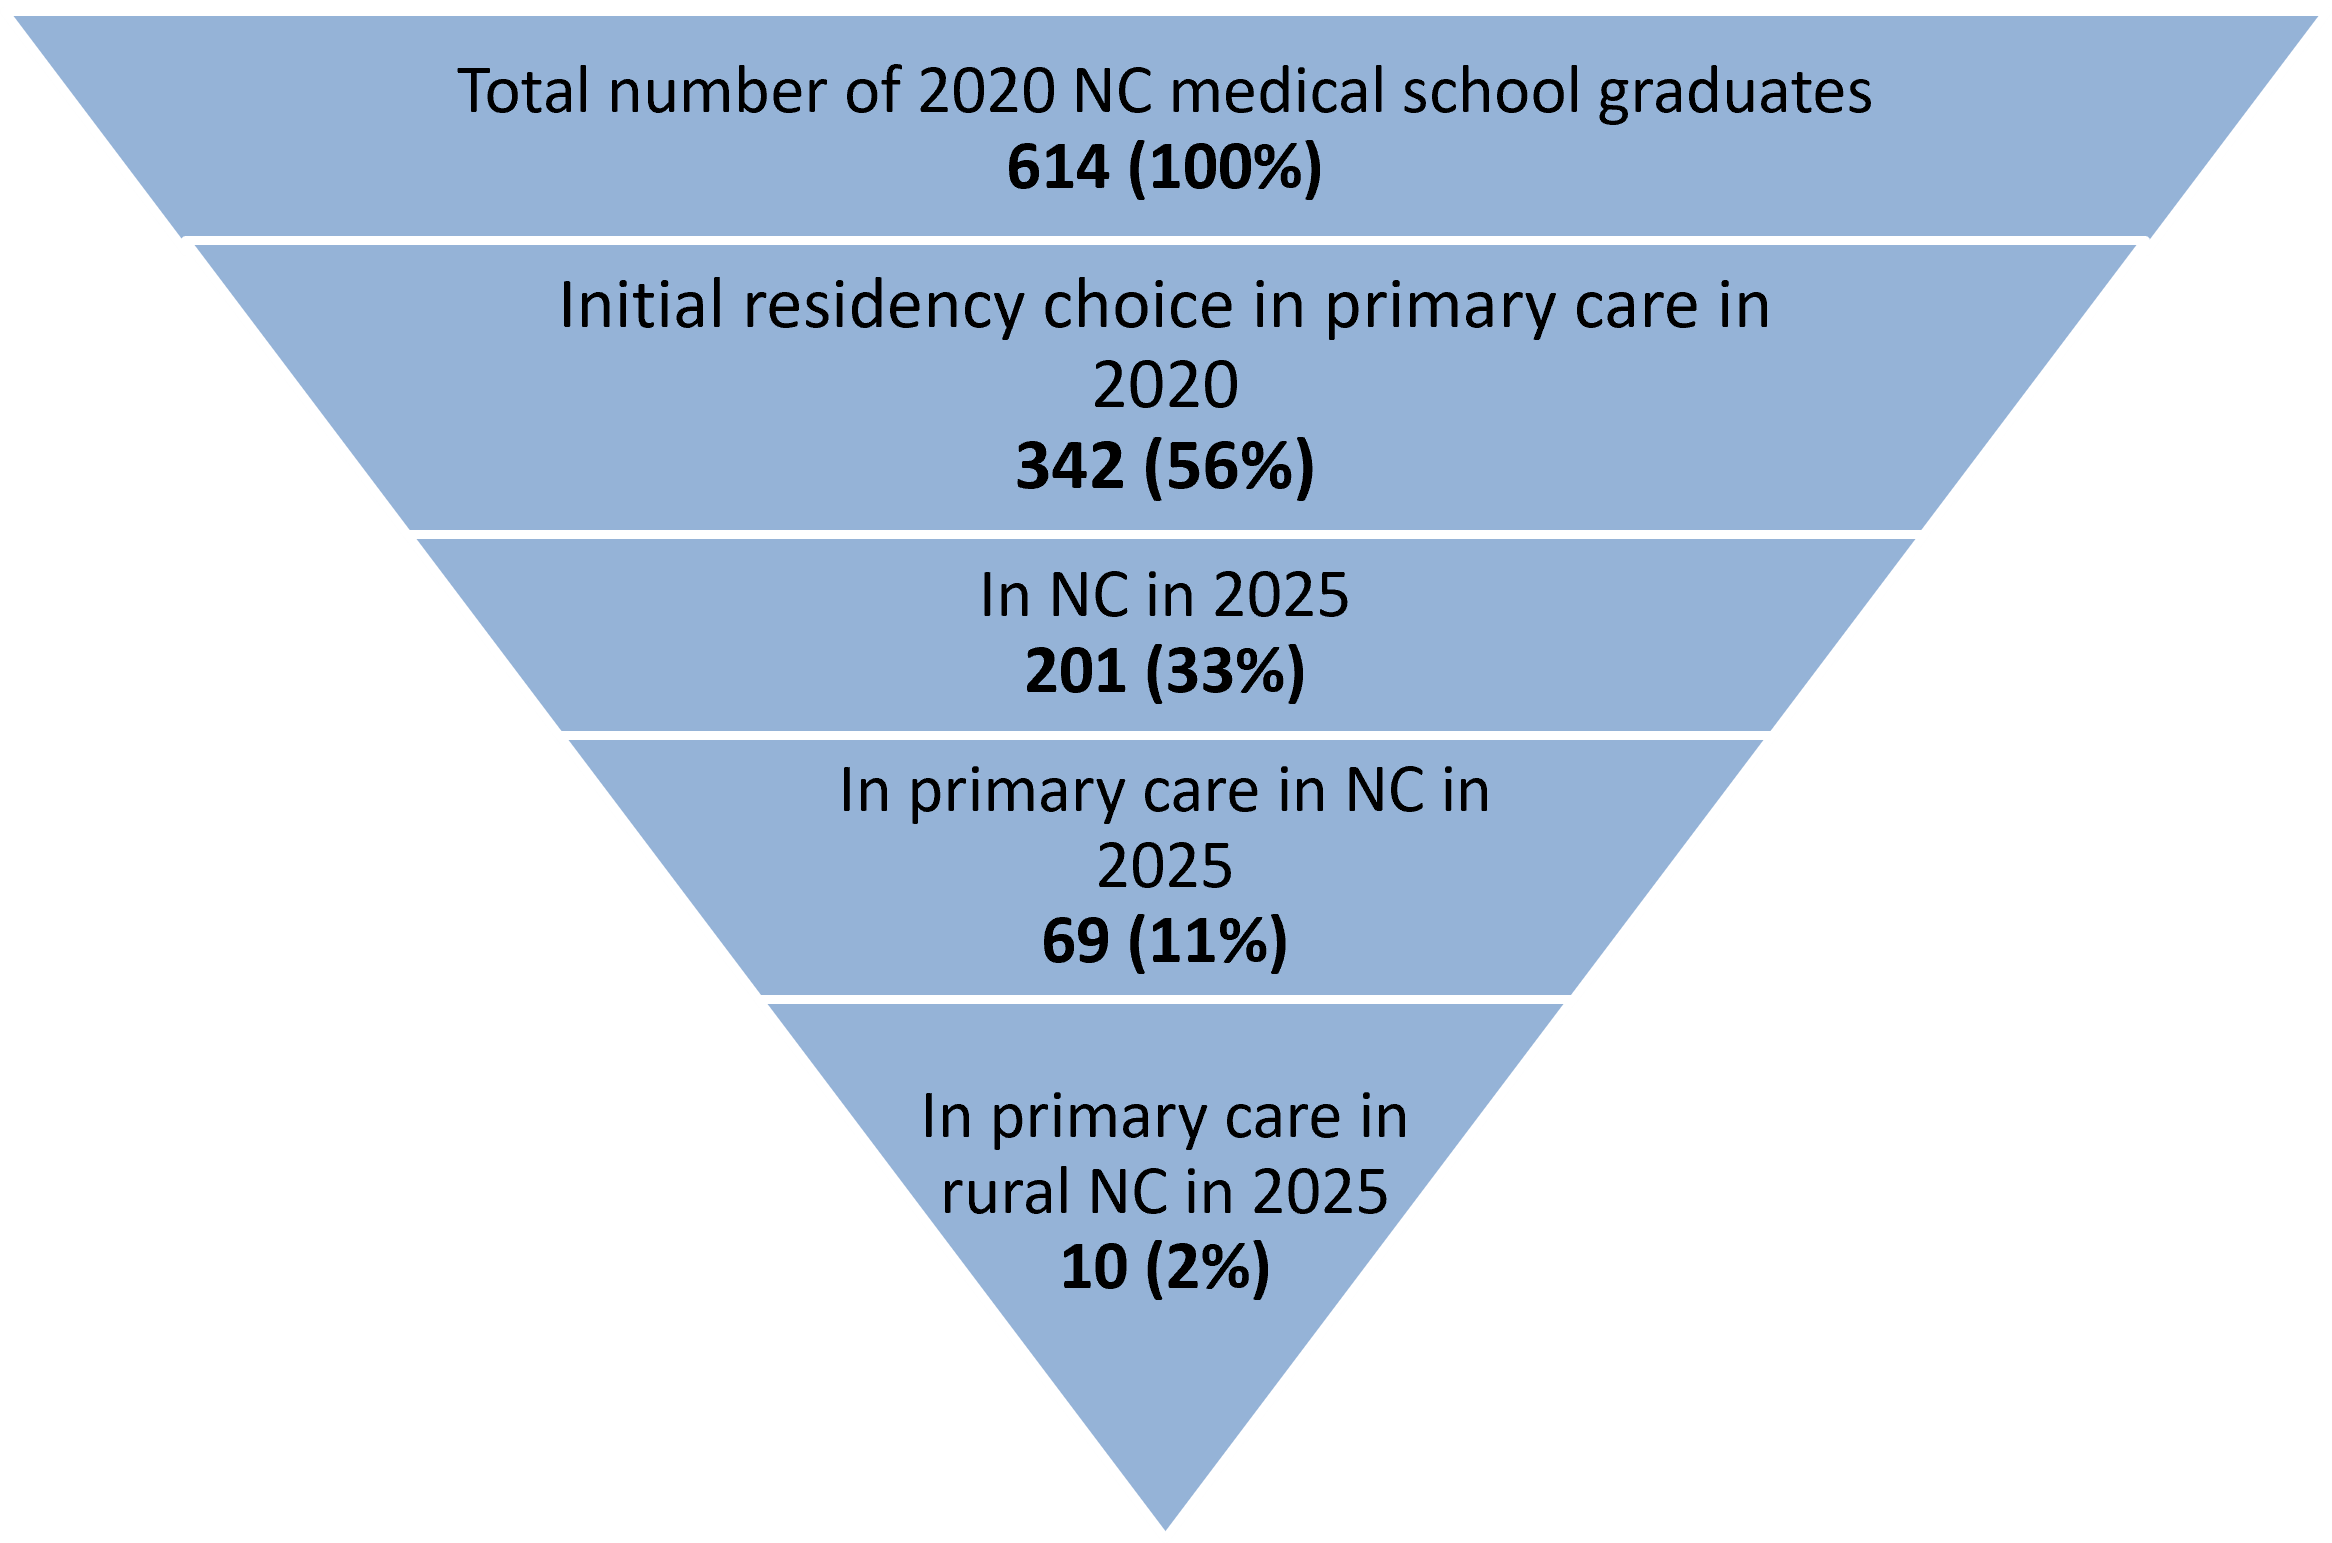
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. Figure data can be accessed here.
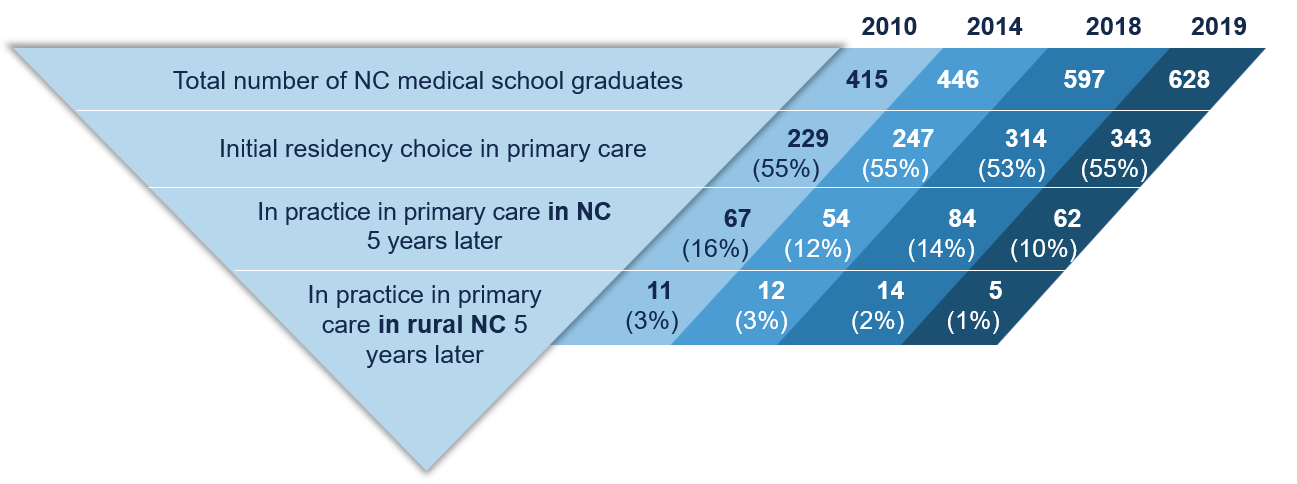
Figure 2 presents historical trends in North Carolina medical student tracking. Although the 11% of the 2020 graduates in training or practice in primary care in NC five years after graduating is an increase from 62 (10%) of 2019 graduates, this is still lower than prior years which were between 12% and 16% of graduating cohorts (the classes of 2010, 2014, and 2018) (Figure 2).
Figure 2. Retention of NC Medical School Graduates in NC, Primary Care and Rural Areas Five Years After Graduating, Selected Classes (2010, 2014, 2018, 2019)
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. Figure data can be accessed here.
The 2020 cohort had 10 graduates in primary care in a rural NC county in 2025, double the number of graduates (n=5) in primary care in rural NC counties from the 2019 cohort in 2024. This modest increase from the 2019 cohort is within the range of previous years when between 1% and 3% of NC medical school graduates were in practice in primary care in rural NC five years after graduating.
Figure 3 presents the percentage of medical student graduates retained in North Carolina five years after graduation by in-state medical schools. A greater percentage of graduates from the state’s public medical schools are retained in NC five years after graduating, compared to the state’s private medical schools (Figure 3). For the class of 2020, 41% of UNC-CH graduates and 36% of ECU graduates were practicing in-state in 2025.
Figure 3. Percent of NC Medical School Graduates in Training or Practice in North Carolina Five Years After Graduating by Medical School, 2008-2020
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC. Figure data can be accessed here.
Figure 4 shows workforce outcomes for each medical school’s 2020 graduate cohort five years after graduating. Each individual figure is a version of Figure 1 for each school’s graduates. Very few graduates from any medical school are practicing primary care in rural areas five years later. ECU increased the percentage of graduates practicing primary care in rural areas of NC to 4% (n=3) in 2025, a small increase compared to 1.4% (n=1) of 2019 cohort graduates in rural NC. ECU and UNC-CH had the largest proportions of graduates practicing in primary care in NC five years after graduating in 2020 (16% and 15%, respectively).
Figure 4. Physician Workforce Outcomes Five Years after Graduation, 2020 Medical School Graduates by School
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. Figure data can be accessed here.
Figure 5 shows, for physicians retained in primary care in NC five years after graduation, the level of distress facing the neighborhoods where they practice. Low scores indicate low levels of economic distress, and high scores indicate high levels of economic distress. Of the 69 graduates from the class of 2020 who were in primary care in NC five years after graduation, 32% (n=22) worked in a practice located in the most economically distressed neighborhoods (ReADI 9 and 10).
Figure 5. Area Disadvantage Status in 2025 of Physicians Retained in North Carolina in Primary Care Who Graduated from a NC Medical School in 2020 (n=69)
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. The Reproducible Area Deprivation Index (ReADI) Score obtained from the Department of Epidemiology and Population Health at Stanford University. Reproducible Area Deprivation Index downloaded from https://sepi.stanford.edu/data-code-publications on March 24, 2026. Figure data can be accessed here.
More about the use of the ReADI
Note: This report uses the Reproducible Area Deprivation Index (ReADI), which is a better measure of socioeconomic distress than used in previous reports. Therefore, distressed-neighborhood percentages should not be compared directly between reports.Retention in North Carolina and Rural Practice by Primary Area of Practice, 2020 Graduates
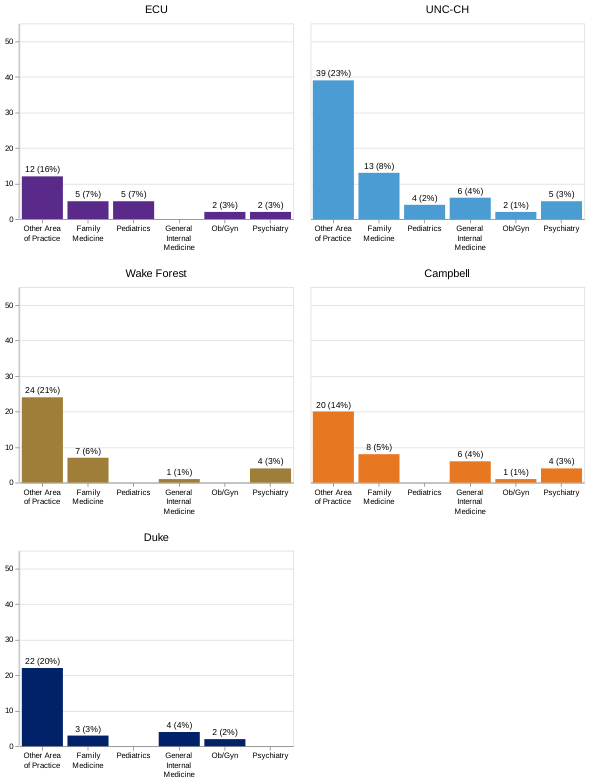
Table 1 displays the number and percent of all 2020 graduates (n=614) that were retained in NC (n=201) and in practice in a rural area in NC (n=16) by area of practice. A physician’s primary area of practice is self-reported during their annual licensure renewal and reflects what they “normally do” in their practice; thus, it may differ from their training specialty. The category “Other Area of Practice” includes all other specialties, including, for example, dermatology, hospitalists, and ophthalmology.
Table 1. Percentage of 2020 Medical School Graduates Practicing or Training in North Carolina by Area of Practice in 2025, North Carolina Overall and Rural
| Area of Practice | Practicing in NC, n (% of total 2020 graduates) | Practicing in rural NC, n (% of total 2020 graduates) |
|---|---|---|
| Family Medicine | 36 (5.9%) | 9 (1.5%) |
| Pediatrics | 9 (1.5%) | 1 (0.2%) |
| Internal Medicine | 17 (2.8%) | 0 (0.0%) |
| Ob-Gyn | 7 (1.1%) | 0 (0.0%) |
| Psychiatry | 15 (2.4%) | 0 (0.0%) |
| Other Area of Practice | 117 (19.1%) | 6 (1.0%) |
| Total in NC | 201 (32.7%) | 16 (2.6%) |
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. For the class of 2020, general surgeons are included in Other Area of Practice.
Figure 6 shows the same set of practice outcomes but for each school individually.
Figure 6. Percentage of 2020 Medical School Graduates Practicing or Training in North Carolina by Medical School and Area of Practice in 2025
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Figure data can be accessed here.
Table 1 and Figure 6 display data only on individuals who were licensed in NC in 2025. While NC medical school graduates may be practicing in distressed areas or in needed areas of practice in other states, this report specifically focuses on outcomes within NC. Consequently, the 413 graduates (67% of the total 2020 class) who were practicing or training in another state, or who were not licensed in NC in 2025, are excluded from Table 1 and Figure 6. However, the percentages shown in the figures represent each group’s proportion of the total 2020 graduating class of 614 students, not just those who remained in NC. As a result, the percentages across all categories sum to 32.7%, not 100%.
Class of 2015 Ten-Year Outcomes
We also tracked the 2015 graduates of NC medical schools to determine where graduates were ten years after graduating from medical school (Figure 7). As noted previously, ten years post-graduation from medical school allows time for physicians to complete residency and fellowship training and settle into practice.
Figure 7. Retention of 2015 NC Medical Graduates in NC, Primary Care and Rural Areas Ten Years After Graduating
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. Figure data can be accessed here.
The total number of graduates in 2015 is lower than in 2020, because Campbell had not yet graduated its first class in 2015. Although a higher percentage (13%) of the 2015 cohort graduates were in primary care in NC ten years after graduation compared to 11% five years after graduation for the 2020 cohort, the 2020 cohort had more graduates overall and a higher number of graduates in primary care in NC five years after graduation (n=69) compared to the 2015 cohort ten years after graduation (n=58). Only 2% (n=8) of 2015 graduates were in primary care practice in rural NC ten years after graduation, the same percentage as five years after graduating for the 2020 cohort.
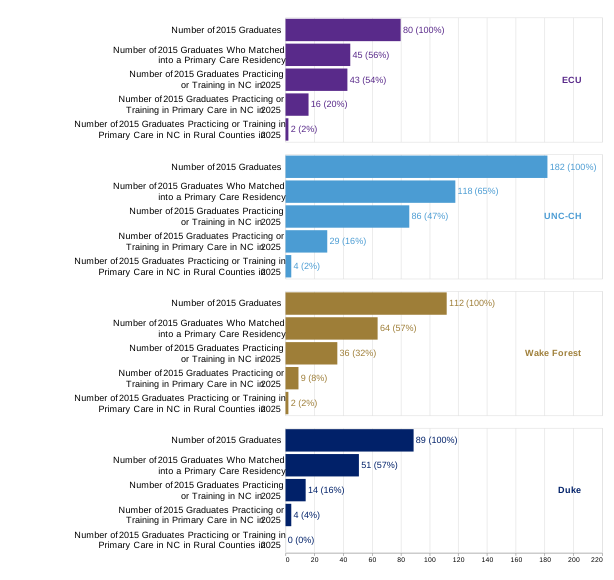
The ten-year workforce outcomes for each school’s 2015 graduates are illustrated in Figure 8. Each individual figure is a version of Figure 7 for each school’s graduates. Very few 2015 graduates from any school practiced in primary care in rural areas ten years after graduation. ECU had the highest percentage of 2015 graduates in primary care in NC (n=16; 20%) but UNC-CH had the largest number of 2015 graduates in primary care practice in NC (n=29) ten years later. ECU, UNC-CH and Wake Forest all contributed about 2% of their graduates to primary care practice in rural areas whereas none of Duke’s graduates were in primary care practice in rural areas 10 years after graduating.
Figure 8. Workforce Outcomes Ten Years after Graduation, 2015 Medical School Graduates by School
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. Figure data can be accessed here.
Practice in Safety Net Settings and Economically Distressed Neighborhoods
Safety net providers are defined as health care facilities that provide a significant amount of health care and other health-related services to uninsured, Medicaid, and other vulnerable populations. Five graduates from the class of 2020 were in practice in safety net settings in NC in 2025, including three UNC-CH graduates, one Duke graduate, and one ECU graduate. Another five graduates from the class of 2015 were in practice in safety net settings in North Carolina in 2025 (Table 2), all from UNC-CH.
Table 2. Medical School Graduates Practicing or Training in Safety-Net Settings in 2025, Classes of 2015 and 2020
| 2015 + 2020 combined | Class of 2015 | Class of 2020 | |
|---|---|---|---|
| Graduates | 1077 | 463 | 614 |
| Practicing or training in NC | 380 | 179 | 201 |
| At safety-net facility | 10 | 5 | 5 |
| % of NC-retained at safety-net facility | 2.6% | 2.8% | 2.5% |
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025.
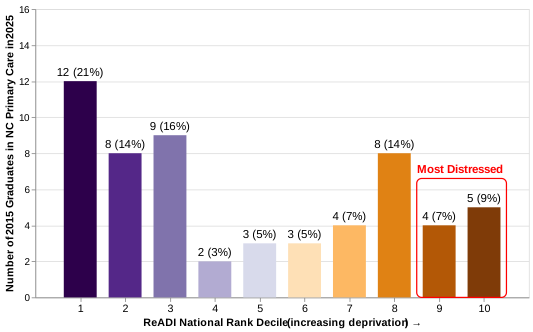
Figure 9 shows the level of distress facing the neighborhoods where 2015 graduates were in practice in primary care in 2025. Low scores indicate low levels of economic distress, and high scores indicate high levels of economic distress. Sixteen percent (n=9/58) worked in a practice location in the most economically distressed neighborhoods (ReADI=9 or 10).
Figure 9. Area Disadvantage Status in 2025 of Physicians Retained in North Carolina in Primary Care Who Graduated from a NC Medical School in 2015 (n=58)
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. ReADI Score obtained from the Department of Epidemiology and Population Health at Stanford University. Reproducible Area Deprivation Index downloaded from https://sepi.stanford.edu/data-code-publications on March 24, 2026. Figure data can be accessed here.
More about the use of the ReADI
Note: As with Figure 5, this report uses the Reproducible Area Deprivation Index (ReADI), which is a better measure of socioeconomic distress than used in previous reports. Therefore, distressed-neighborhood percentages should not be compared directly between reports.Retention in North Carolina and Rural Practice by Primary Area of Practice, 2015 Graduates
Table 3 shows the number and percent of all 2015 graduates (n=463) who were retained in NC (n=179) and in practice in a rural area in NC (n=10) ten years after graduating. A physician’s primary area of practice is self-reported during their annual licensure renewal and reflects what they “normally do” in their practice; thus, it may differ from their training specialty. The category “Other Area of Practice” includes all other specialties, including, for example, dermatology, hospitalists, and ophthalmology. Of the 179 2015 graduates who were retained in NC ten years after graduation, 23 were in family medicine, 13 in pediatrics, 12 in general internal medicine, 10 in ob-gyn, 4 in general surgery and 10 in psychiatry. The rest (n=107) went into other specialties. The outcomes for general surgery are reported here for the 2015 cohort, but not for the 2020 cohort, because general surgery residencies typically last five years, and many general surgeons complete a subspecialty fellowship afterwards. For this reason, reporting on general surgery practice outcomes at five-years post-graduation may be misleading. Of the 10 physicians retained in rural areas ten years later, 5 had a primary area of practice in family medicine.
Table 3. 2015 Medical School Graduates Retained in North Carolina by Area of Practice in 2025, Retention in North Carolina and in Rural Areas
| Area of Practice | Practicing in NC, n (% of total 2015 graduates) | Practicing in rural NC, n (% of 2015 graduates) |
|---|---|---|
| Family Medicine | 23 (5.0%) | 5 (1.1%) |
| Pediatrics | 13 (2.8%) | 1 (0.2%) |
| Internal Medicine | 12 (2.6%) | 1 (0.2%) |
| Ob-Gyn | 10 (2.2%) | 1 (0.2%) |
| General Surgery | 4 (0.9%) | 0 (0.0%) |
| Psychiatry | 10 (2.2%) | 0 (0.0%) |
| Other Area of Practice | 107 (23.1%) | 2 (0.4%) |
| Total in NC | 179 (38.7%) | 10 (2.2%) |
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Rural source: Federal Office of Rural Health Policy (FORHP) rural delineation files, retrieved March 2026 from https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files.
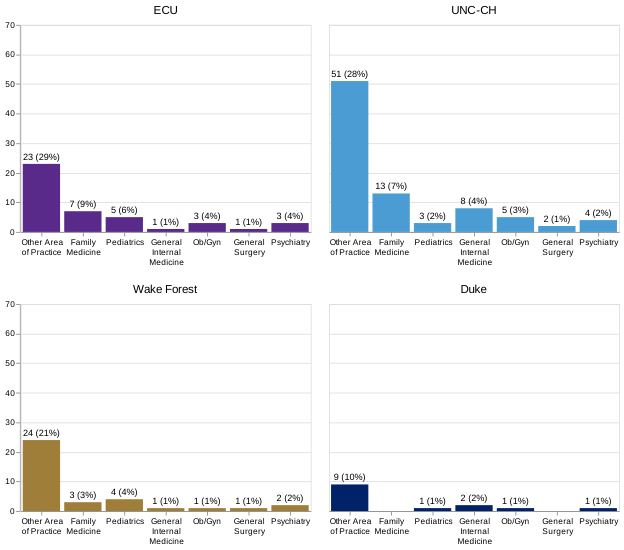
Figure 10 shows, for each medical school, the percentage of 2015 graduates in practice or training in NC by area of practice.
Figure 10. Percentage of 2015 Medical School Graduates Practicing or Training in North Carolina by Medical School and Area of Practice in 2025
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: North Carolina Health Professions Data System with data derived from the NC Medical Board and the AAMC, 2025. Figure data can be accessed here.
Table 3 and Figure 10 include only individuals who were licensed in North Carolina in 2025. While 2015 graduates may be practicing in distressed areas or in needed areas of practice in other states, this report specifically focuses on service within North Carolina. Consequently, the 284 graduates (61% of the total class) who were practicing or training in another state, or who were not licensed in NC in 2025, are excluded from these charts. However, the percentages shown in the figures represent each group’s proportion of the total graduating class of 463 students, not just those who remained in North Carolina. As a result, the percentages across all categories total only 38.7%, rather than 100%.
Initial Match Data: 2025 Graduating Cohort
This report does not emphasize the outcomes of the initial match data for graduates from NC medical schools as residents may switch specialties during their training, and many subspecialize. The outcome data that report on a physician’s practice status after five or ten years post-graduation are more accurate in estimating the workforce outcomes for each medical school. Initial matches to “primary care” specialties (family medicine, internal medicine, pediatrics, internal medicine-pediatrics, and obstetrics & gynecology) are inflated compared to the number of graduates who eventually practice in those fields. We also track two other needed specialties in NC: psychiatry and general surgery. Prior trends indicate that many NC graduates, including most of those who match to Internal Medicine and General Surgery, will go on to complete fellowship training and eventually practice in a subspecialty field. For instance, 133 graduates from 2015 trained in internal medicine, but 82% went on to pursue training in a subspecialty or another specialty (not including geriatric medicine). Family medicine is the exception: of the 44 graduates who trained in family medicine, none pursued training in another specialty, and only two completed fellowships (geriatric medicine).
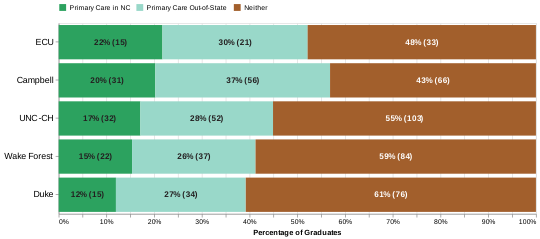
Figure 11 shows the proportion of each school’s 2025 graduates who had an initial match to a primary care residency in NC or in another state. Across the five schools 315 of 677 graduates (47%) initially matched into primary care with 115 (17%) matching into primary care in North Carolina. ECU matched the greatest proportion to primary care residencies in NC (22%, n = 15). However, Campbell and ECU both matched more than 50% of their graduates to primary care residencies, including both in-state and out-of-state matches.
Figure 11. Initial Matches of 2025 Medical School Graduates to Primary Care Residencies by School
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: the respective medical schools, 2025. Figure data can be accessed here.
Figure 12 displays the number of 2025 graduates who matched to primary care specialties, general surgery, or psychiatry. (Note that the axes are scaled to each school’s number of graduates.) ECU and Campbell led on family medicine residency matches, with 6% of ECU’s graduating class matching to a family medicine residency in North Carolina, and 21% of Campbell graduates matching to a family medicine residency anywhere in the US. UNC matched the greatest number (13) of graduates to internal medicine residencies in NC, while ECU matched the greatest percentage (12%, n=8).
Figure 12. Number of 2025 Medical School Graduates by School and Initial Match Specialty, Selected Specialties
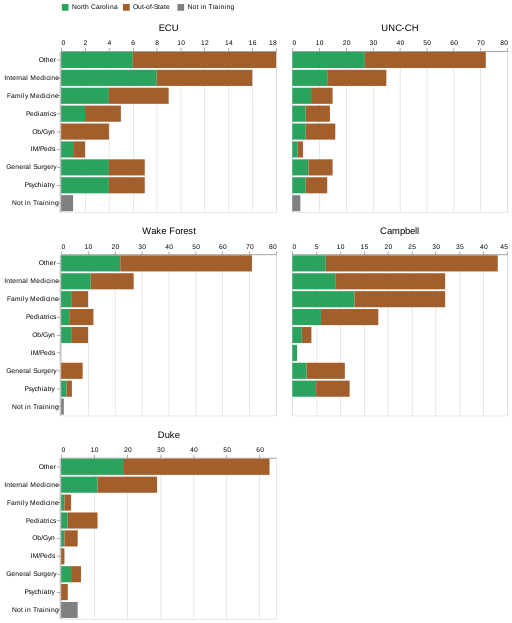
Note. Produced by the Program on Health Workforce Research and Policy, Sheps Center for Health Services Research, University of North Carolina at Chapel Hill. Source: the respective medical schools, 2025. Figure data can be accessed here.
Discussion
This report showed that of the 614 medical school graduates from North Carolina’s five medical schools in 2020, 11% were in primary care in NC in 2025 five years after graduation. Compared to previous reports, the percent of medical graduates practicing in primary care continues to decline, decreasing from 16% of the 2010 graduating cohort to 11% of the 2020 graduating cohort (Figure 2). The percentage of medical graduates practicing in rural areas remains low, hovering around 1-3% between 2010 and 2020. A greater percentage of graduates from the state’s public medical schools are retained in NC five years after graduating, compared to the state’s private medical schools.
A higher percentage of graduates are retained in NC and in primary care practice ten years after graduation compared to five years after graduation. This may suggest that NC medical school graduates are leaving the state for residency training but then returning after pursuing residency training out of state or that previously implemented interventions are beginning to have more long-term effects.
It is important to consider this report’s findings that relatively few NC medical students end up in primary care specialties in the context of broader workforce trends in the US. National data show a declining proportion of medical school graduates and residents entering primary care careers.2 For example, the percentage of graduating internal medicine residents planning a career in general internal medicine has declined by half in the last decade.8 Concurrently, the growth of hospitalists and the declining number of internal medicine physicians trained, and practicing, in community-based settings has reduced the number of primary care physicians choosing community-based primary care medicine. Pediatrics and family medicine face similar challenges.9 Between 2023 and 2024, general pediatrics’ fill rate for residency training declined from 97.1% to 91.8% and although it rebounded slightly, remains at 94.4% in 2026. In 2026, family medicine offered 5,491 positions, 134 more than offered in 2025. However, the fill rate declined from 85.0% to 83.6% and the number of U.S. MD seniors matching into family medicine remains significantly below historical trends.
Also important for contextualizing the findings in this report is the fact that a physician’s training pathway is long and medical school is just one point in their career trajectory. Where a physician completes residency training is a better predictor of where they will end up in practice than medical school location. Physicians who complete residency training in rural areas and community-based settings are more likely to choose rural, primary care careers.3,4,5 North Carolina data underscore these findings.6 The number of physicians completing residency training in North Carolina increased from 1,145 in 2017 to 1,264 in 2019. On average, just 37% of these graduates were retained in active practice in NC five years after graduation and 3% were in rural communities. However, nearly 65% of physicians who completed both medical school and residency training were retained in-state after five years, underscoring the return on investment of building pathways from medical school to residency training in the state. The retention rate for family medicine is even higher; 88% of family medicine physicians who completed both medical school and residency training in NC remain in-state and 20% remain in practice in rural areas five years after finishing residency training.
The health care system has also undergone dramatic changes in the last thirty years and the data in this report remain as critical as ever to help inform the state’s efforts to address chronic shortfalls of primary care physicians, especially in rural areas.
Suggested Citation: Galloway E, Fraher E, Tarr N, Moore C, Tilson HH. Monitoring the Workforce Outcomes of North Carolina Medical School Graduates: Retention In-State and in High Need Geographic Areas and Specialties. Cecil G. Sheps Center for Health Services Research. The University of North Carolina at Chapel Hill. August 14, 2026.
Appendix
Appendix A
Data Sources and Methods
Data Sources
Data included in this report come from several sources:
- The North Carolina Medical Board’s (NCMB) annual licensure files, maintained by the NC Health Professions Data System at the Cecil G. Sheps Center for Health Services Research
- GMETrack, the graduate medical education tracking file of the Association of American Medical Colleges (AAMC)
- Data from the alumni and student affairs offices at the Campbell University School of Osteopathic Medicine, the Duke University School of Medicine, the Brody School of Medicine at East Carolina University, the University of North Carolina at Chapel Hill School of Medicine, and the Wake Forest University School of Medicine
- The Federal Office of Rural Health Policy (FORHP) rural delineation files retrieved March 2026 at https://www.hrsa.gov/rural-health/about-us/what-is-rural/data-files. This is the definition of rural used in this report.
- The NC Department of Health and Human Services (DHHS) list of safety net sites, updated in July 2024.
- The 2022 vintage of the Reproducible Area Deprivation Index (ReADI) produced by the Department of Epidemiology and Population Health at Stanford University.
Campbell University School of Osteopathic Medicine (Campbell) is not mandated to provide data for this report, as the school did not exist when the 1993 legislation was passed. However, Campbell has provided initial match data for the last several years and now has its fourth five-year cohort reported in this report.
Methods
We merged GMETrack data from the AAMC for 2015 and 2020 medical school graduates with the 2025 NCMB annual licensure file (housed with the Health Professions Data System) to determine physician practice outcomes at five or ten years post-graduation from medical school. The NCMB’s licensure data provides in-state practice locations and areas of practice, while the GMETrack data from the Association of American Medical Colleges (AAMC) is the source list for graduates within a cohort.
Primary care residency specialties are defined by legislation passed by the NC General Assembly in 1993 (Senate Bill 27/ House Bill 729) and include family medicine, general internal medicine, general pediatric medicine, internal medicine-pediatrics, and obstetrics & gynecology. Even though internal medicine-pediatrics is not reported as an area of practice by the NCMB, physicians trained in internal medicine-pediatrics typically report either pediatrics or general internal medicine as an area of practice and are therefore still captured as primary care physicians in the report.
“Primary Care” is defined for both initial specialty of residency training (identified in GMETrack data for each cohort) and for current practice or training area (identified using NCMB data for physicians in NC). As discussed above, many graduates who initially match to internal medicine and are counted as primary care for their initial match to residency training will go on to train and practice in subspecialties outside of primary care five years after graduation. As a result, the number of medical students matching to primary care for their initial residency choice is overstated relative to the number of physicians who will end up practicing in primary care.
Psychiatry includes physicians who report practicing in the following specialties: psychiatry, child and adolescent psychiatry, psychoanalysis, forensic psychiatry, psychosomatic medicine, psychiatry/geriatric, family medicine-psychiatry, internal medicine-psychiatry, and pediatrics-psychiatry.
Based on clinical input and methods in previous analyses, general surgery includes physicians who report practicing in the following specialties: general surgery, abdominal surgery, colon & rectal surgery, critical care surgery, head and neck surgery, oncology surgery, pediatric surgery, transplant surgery, trauma surgery, or vascular surgery.
For safety net provider information, we geocoded both the North Carolina Department of Health and Human Services safety net site list and the practice addresses in the NCMB file for each cohort. We then intersected the geocoded datasets to find potential matches between providers and sites. Potential matches were manually checked for accuracy. Safety net providers are defined as health care facilities that provide a significant level of health care and other health-related services to uninsured, Medicaid, and other vulnerable populations. These include rural health clinics, rural health centers, federally qualified health centers, free and charitable clinics, small rural hospitals, health departments, and critical access hospitals. We also used the geocoded locations to place each physician in a census tract, allowing us to assign each to an area deprivation index.
The Reproducible Area Deprivation Index (ReADI) is a measure that summarizes the socioeconomic distress of a census tract using data from the American Community Survey.10,11 The ReADI is based on factors related to income, education, employment, and housing quality in a census tract, which is the geographic equivalent of a neighborhood. The index uses 17 different measurements across a range of domains, like “Percent of households without a motor vehicle” and “Percent of population aged >= 25 years with a high school diploma”. The weights from a factor analysis of these variables are used to calculate a score for each tract, which is then converted to a national-rank decile for each census tract.
To define rural in this report, we use the Federal Office of Rural Health Policy’s definition.
To report initial residency match data for 2025, we asked each of the medical schools in the state to submit aggregate match data for these recent graduates, which they provided via email.
Appendix B
Below are self-reported responses from each North Carolina medical school about their efforts to increase the number of students who will practice primary care in rural North Carolina.
Campbell University School of Osteopathic Medicine
The mission of the Campbell University School of Osteopathic Medicine (CUSOM) is to educate and prepare community–based osteopathic physicians in a Christian environment to care for the rural and underserved populations in North Carolina, the Southeastern United States, and the nation. The focus on community-based care is significant as it recognizes the unique health care needs of rural and underserved populations. The preparation to enter those environments is unique and has been a core focus for our school. The Christian environment that we foster has played a significant role in shaping the values and beliefs of our graduates and shaping the way they approach their work as physicians. By instilling a strong sense of compassion, empathy, and ethical principles in its graduates, CUSOM is helping to ensure that they are well-prepared to provide high-quality, patient-centered care that is consistent with institutional values.
Campbell University School of Medicine opened its doors to its inaugural class of 162 students in 2013. Campbell University also became the first College of Osteopathic Medicine to serve as an ACGME sponsoring institution for Graduate Medical Education. As a sponsoring institution, Campbell University has provided support and resources to its affiliated residency programs ensuring that they meet the standards and requirements set forth by the ACGME. 15 osteopathic programs successfully transitioned to ACGME accreditation under Campbell University’s Sponsoring Institution. Campbell University now serves as the Sponsor for 11 ACGME-accredited programs in partnership with 3 hospitals and systems. We serve as an educational affiliate partner for 4 additional hospital systems in NC.
Medical Student Impacts
The graduating class of 2017 (our inaugural class) would have completed 3-year residencies in 2020, 4-year residencies in 2021, and 5-year residency programs in 2022.
The graduating class of 2018 would have completed 3-year residencies in 2021, 4-year residencies in 2022, and 5-year residency programs in 2023.
The graduating class of 2020 would have finished their 5-year residencies in 2025.
According to the data that we have on the first four classes and partial for 2019 and 2020, 410 of our graduates are currently in practice in southeast US with 225 of those graduates located in the state of North Carolina. Trends suggest that CUSOM is making a positive contribution to the development of the physician workforce in North Carolina and that its graduates are well-prepared to enter the workforce and provide high-quality care to patients. The strong commitment to primary care fields and specific areas of need is critical to positively impacting our state’s ability to provide comprehensive, patient-centered care.
Graduate Medical Education Impacts
Campbell University had a goal of having a net neutral impact on the number of graduate medical education positions by creating enough positions that we would not graduate more medical students than the graduate medical education positions we created. To date, Campbell University has started 25 residency and fellowship programs in North and South Carolina. And as of 2026, we have transitioned to serving as an educational affiliate for the Cape Fear Valley, UNC Heath Southeastern, and Hugh Chatham programs while assisting Cape Fear Valley and UNC Health Southeastern sites with becoming their own sponsoring institutions. Our current programs contain 120 GME positions in Family Medicine (x3), Internal Medicine, Dermatology, and Transitional Year (x3). We have fellowship programs in Sports Medicine (x2) and Micrographic Surgery.
Campbell University had our first resident start in 2014 as an educational partner through the AOA. Since that time, Campbell University Graduate Medical Education programs have placed over 80 providers into active clinical practice with roughly 38% of those remaining in North Carolina and roughly 59% being in the fields of Family Medicine or Internal Medicine. Primary care is a critical component of health care, as it provides the foundation for patient care and helps to manage the overall health and well-being of individuals and populations. A solid primary care workforce is essential to ensuring that patients have access to comprehensive, high-quality care and that health care systems can effectively address the health needs of their communities.
Summary
Campbell University Graduates are now currently active in 47 of North Carolina’s 100 counties. The full impact of Campbell University graduates to the physician workforce is still emerging. 2020 saw the inaugural class graduate from 3-year primary care programs. 2022 saw the first graduates in Surgery and Psychiatry from Campbell University GME programs. Combining the efforts of our medical school and our graduate medical education programs, Campbell University has placed new providers in 47 North Carolina counties as of April 2025. Additionally, 30 of the 47 occupied North Carolina counties are underserved, which displays that Campbell University is meeting its mission of producing graduates to work in rural and underserved counties.
Duke University School of Medicine
Duke provides medical student clinical rotations. The goals of this program are for students to learn clinical skills in the context of a local community and to appreciate the effects of culture and context on health and health behaviors. Duke students may rotate through clinics in Person and Durham County health departments evaluating and following patients in these rural communities.
Duke also offers the Primary Care Leadership Track (PCLT), the goal of which is to create change agents for the system through primary care and leaders in the health care profession. The 4-year program offers leadership training, a longitudinal-integrated 2nd year clerkship, which includes following pregnant mothers and delivering their babies, time for service with a community agency, and 3rd year research in community-engaged population health. PCLT graduates have chosen primary care residencies: family medicine (outpatient adults, children, and prenatal care), general internal medicine (adults only), primary care pediatrics (children only), pediatrics/psychiatry, medicine/psychiatry, family medicine/psychiatry and Obstetrics/gynecology.
Through our MS1 reflection exercises and lunch discussions, specialty handbook, and specialty advisor community, the Career Exploration and Career Destination program helps our students identify the values and skills that will be most meaningful to them in clinical practice and match that with the correct specialty, including those rooted in the delivery of primary care.
Duke offers a primary care student interest group open to all students that has career panels 1-2 times a year and meets regularly.
ECU Brody School of Medicine
Brody School of Medicine (BSOM) stands apart with its three-part mission to increase the supply of primary care physicians serving the state, improve the health and well-being of the region, and train physicians who will meet the state’s health care needs. This distinctive mission makes BSOM a top choice for those intending to practice primary care specialties in our state.
Residency Match and Future Practice
The success of our students is a testament to the quality of education at BSOM. With over 400 graduates in the last five years, and more than half of them practicing primary care. We continue to see this pattern in our recent Class of 2026, with 53% of our graduates matching in primary care and 41% in North Carolina, serving our communities. As a result, BSOM continues to be ranked above the 90th percentile nationally in the percentage of graduates practicing primary care and in-state, as well as in the Top 35 medical schools with the most graduates practicing in medically underserved areas.
Medical Curriculum
Match outcomes reflect our medical curriculum. Starting in the foundational years of the curriculum, BSOM medical students are expected to participate in and complete primary care activities at community sites, mostly in Eastern North Carolina.
During the second year, students are scheduled with preceptorship dates every fall to shadow and work with physicians and health professionals at North Carolina practices (only in-state practices are approved). As students progress in the medical curriculum, our Family Medicine, Internal Medicine, and Pediatrics clerkships have allocated two to four weeks in their schedules for students to spend time practicing with affiliated faculty at local and statewide community sites, mostly in ambulatory clinics. Additionally, students can choose from over 170 electives in the third and fourth years of the medical curriculum, of which more than half of these experiences are in primary care specialties. These elective courses give our students additional opportunities to interact with other professionals and community resources, mainly in North Carolina and the Eastern region of our state, to provide comprehensive and continuing care, and to work with different types of care delivered in other settings and populations outside the university medical center.
These experiences have made BSOM graduates confident that they have acquired the technical skills needed to begin a residency program, feel prepared to care for patients from different backgrounds, and have the communication skills necessary to interact with patients and health professionals. As a result, over 90% of BSOM graduates in primary care residencies are rated as meeting or exceeding expectations in their first year of the residency program.
Service and Research
In addition to curricular and learning measures that focus on primary care and early immersion in patient care experiences, non-curricular events and programs have been created to enable students to interact with primary care practitioners.
The BSOM Distinction Track Program allows medical students to pursue an area of interest in their medical career independently. The program has five tracks aligned with our missions: health system transformation and leadership, medical education and teaching, research, service learning, and medical humanities and ethics. While in the program, medical students work with faculty mentors on a longitudinal project that culminates as a capstone in the fourth year of the curriculum. Many projects are in primary care specialties, with primary care clinicians, in topics that relate to our population in eastern North Carolina, and improvements to the health and well-being of our region. The following are examples of past and in-progress projects for some of the tracks:
- Right Care at the Right Location: Retrospective Review
- Comparing prehospital time among pediatric poisoning patients in rural and urban settings
- HANDS-On Childhood Health Education – PhysioCamp Early STEM Engagement in Pitt County
- Structured Documentation of Child Abuse History After Treatment of Pediatric Patients for Confirmed or Suspected Child Maltreatment
- Medical Respite: Shelter for Medically Fragile People Experiencing Homelessness
Our medical students volunteer at various free clinics in our region, primarily the Pitt County Care Clinic. By graduation, over 80% of BSOM graduates have experience with a free clinic serving underserved populations, expertise in health disparities, and have learned to use an interpreter when needed.
The combination of our medical curriculum, non-curricular experiences, and our students’ desire to pursue primary care specialties and practice in underserved and underrepresented populations is why BSOM continues to be ranked nationally in the 94th percentile of graduates practicing in underserved areas by the AAMC.
Residency Programs
The development and expansion of the Rural Family Medicine Residency Program have been successful in placing more trainees in underserved areas. In July 2024, after ACGME approval, the Rural Family Medicine Residency Program expanded to include a third site in Roanoke Rapids, NC. The program is expected to have 27 residents in training at a given time. As of June 2025, there are 15 Rural Family Medicine residents in training. The Department of Family Medicine, together with the Resident and Fellow Recruitment Program, has worked to recruit graduates from the training program. We have a higher-than-national retention rate of graduates from rural residency programs, 67%. These graduates are working in ECU Health clinics and Rural Family Medicine Residency continuity clinics. Some of them will serve as teaching faculty for the Rural Family Medicine Residency Program, thereby continuing to strengthen the recruitment and experience of the trainees.
To continue increasing the supply of residents matching into our Rural Family Medicine Residency Program, the BSOM, together with ECU Health Graduate Medical Education, will explore a 3-and-3 primary care track, in which medical students complete their medical training in 3 years and match into the Rural Family Medicine Residency Program.
University of North Carolina at Chapel Hill School of Medicine
Our mission is to improve the health and wellbeing of North Carolinians and others whom we serve through excellence in patient care, education, and research. A central part of this mission is training the physician workforce that serves communities across our state.
UNC School of Medicine physician graduates practicing in NC
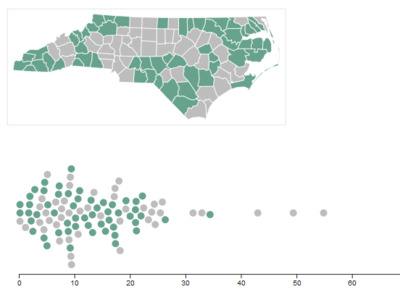
UNC SOM is a key driver of North Carolina’s physician pipeline. Our graduates practice in every region of the state, delivering care across both rural and urban communities (Figure 1). As of 2023, there are nearly 2,700 UNC SOM graduates practicing in 88 counties across the state, and those 88 counties contain 98.3% of the State’s population. Our distribution of our physician alumni across rural and urban counties demonstrates our commitment to ensuring access to care regardless of geography.
Figure 1. Number of UNC SOM physician alumni working in NC counties as of 2023
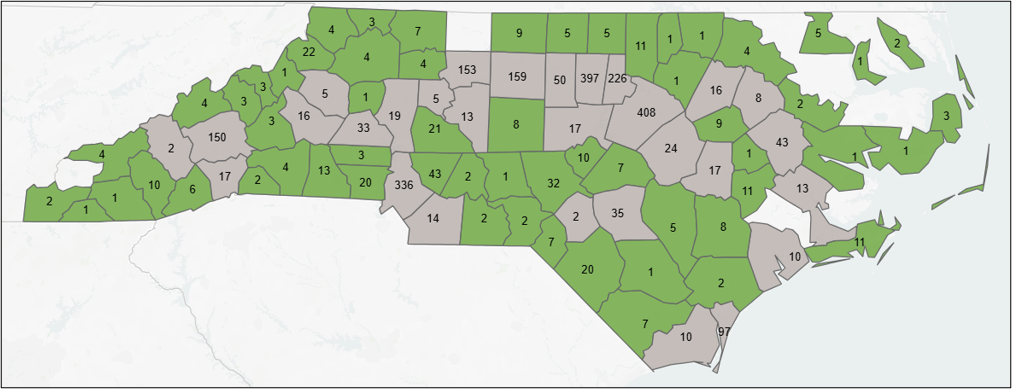
Note. Green = rural counties and gray = urban counties.
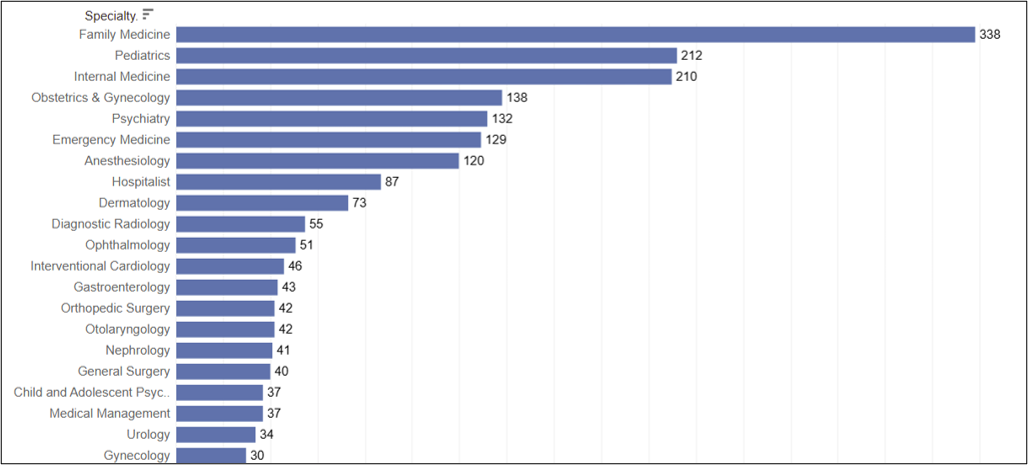
UNC SOM is intentionally aligned with the state’s most pressing healthcare needs, with a strong emphasis on training physicians in primary care. As shown in Figure 2, the largest number of our alumni in North Carolina are practicing in primary care fields, including family medicine (n=338), pediatrics (n=212), and internal medicine (n=210), followed by obstetrics and gynecology (n=138) and psychiatry (n=132). These data underscore UNC SOM’s leadership in producing the primary care workforce that is essential to improving access, managing chronic disease, and supporting population health across the state.
At the same time, North Carolina faces a projected shortage of more than 7,700 physicians by 2030 across both primary care and specialty fields. Addressing this gap requires a comprehensive approach. UNC SOM is committed not only to expanding primary care training, but also to preparing specialists and subspecialists who are critical to delivering high-quality, comprehensive care for all North Carolinians.
Figure 2. UNC SOM physician alumni working in NC by top specialty frequency as of 2023
UNC medical school’s focus on rural and community-based training
To meet these needs, UNC SOM has developed targeted programs that prioritize rural and community-based training, including initiatives within our Community Health Training Program (CHTP), which combines opportunities from two prior programs, Kenan Rural Scholars and FIRST (Fully Integrated Readiness for Service Training). CHTP features:
- Enhanced curriculum focused on Community and Rural Health
- Early and longitudinal clinical exposure with in-depth experiences in rural community practices
- Strong cohort experience with a small group of peers with similar interests and goals
- Strong mentorship from program leadership and community physicians
- Scholarship money tied to specialty, location, and rural intent in North Carolina
- Opportunity to participate in a 3-year accelerated curriculum with a directed pathway to affiliated residency programs followed by three years of service in a rural or underserved area of NC with ongoing support in practice.
These programs are designed to recruit, train, and retain physicians in underserved areas—helping to build a sustainable workforce pipeline for rural North Carolina
UNC medical school graduates remaining in NC for residency training
UNC School of Medicine’s impact on the state’s physician workforce is reflected not only in the growing proportion of graduates who remain in North Carolina for residency training, but also in the substantially higher number of physicians retained each year. A key driver of long-term physician retention is where doctors complete their residency training. Physicians who train in North Carolina are significantly more likely to establish their practices in-state. For this reason, UNC SOM actively encourages graduates to remain in North Carolina for residency and works closely with in-state programs to support this pathway.
Participation in the National Resident Matching Program (“the Match”) represents a critical transition point in this pipeline. UNC SOM has made measurable progress at this stage, with both the percentage and the absolute number of graduates matching to North Carolina residency programs increasing over time:
- 2022: 27% (53/194)
- 2023: 32% (61/193)
- 2024: 37% (63/171)
- 2025: 38% (69/180)
- 2026: 42% (88/209)
Importantly, because UNC SOM has expanded its class size from 190 to 230 per class, these gains translate into a substantially larger number of physicians remaining in the state. In 2026, 42% of the graduating class represents 88 physicians entering North Carolina residency programs—the highest number in recent years. This dual growth—a higher retention rate and a larger graduating class—significantly strengthens the state’s physician pipeline and underscores UNC SOM’s role in addressing North Carolina’s workforce needs. Furthermore, among the 209 graduates, 106 (51%) matched into primary care residency programs.
In summary, UNC SOM is delivering on its commitment to North Carolina by:
- Training physicians who practice in nearly all counties, including rural and underserved areas
- Producing a strong pipeline of primary care physicians, while also addressing specialty needs
- Expanding programs that prepare physicians for rural and community-based practice
- Increasing the number of graduates who remain in North Carolina for residency—an essential step toward long-term retention
Through these efforts, UNC SOM is not only educating future physicians but actively strengthening North Carolina’s healthcare workforce and improving access to care for communities across the state.
Wake Forest University School of Medicine
Wake Forest University School of Medicine (WFUSM) has been continuously accredited since prior to 1942 when the LCME was created. Recognized for its commitment to medical education, research, and healthcare excellence, WFUSM has a rich history of producing exceptional healthcare professionals and impacting care of North Carolinians in the western Carolinas. The MD program is committed to a mission of educating future physicians empowered to transform health for all and is committed to improving the health of individuals and communities through lifelong learning. The school is guided by the University’s motto, Pro Humanitate (for humanity), which anchors teaching priorities within a tradition of humanism in medicine. Below are a selection of programs including curricular and extra-curricular to promote a future physician workforce prepared for the primary care and rural health needs of all communities.
Selected Extracurricular Opportunities for WFUSM Students:
Family Medicine Interest Group: The Wake Forest University School of Medicine Family Medicine Interest Group aims to spark student interest in Family Medicine by promoting patient-centered, holistic care and supporting early exposure through events and mentorship. Inspired by AAFP values, the group advocates for health equity, engages with the local community, and hosts diverse educational workshops—including focused sessions on rural health and obstetrics. Their programming benefits all medical students, fosters leadership, and has helped establish new electives and interest groups dedicated to addressing workforce needs in underserved areas.
Rural Health Student Interest Group: The Rural Health Student Interest Group, launched in the 2025-26 academic year, was created by students to expand student exposure to rural health across medical specialties and foster early engagement with rural practice. At its inaugural meeting, 17 students attended, reflecting strong interest in this area. The group aims to provide a centralized space for students to learn about rural health volunteer opportunities, share information about rural electives and training pathways as they arise, and build meaningful connections with rural physicians across specialties. Through these efforts, the group seeks to support mentorship development and help students explore and prepare for careers serving rural communities.
Share the Health Fair: According to the 2022 Forsyth County SCOTCH Report, the top five intervenable causes of death for the county are cancer, heart diseases, chronic lower respiratory disease, cerebrovascular disease, and diabetes. Share the Health Fair exists to address these health discrepancies and improve health equity in Winston-Salem by minimizing barriers to care, improving social determinants of health, increasing awareness of preventative measures to avoid common chronic diseases, connecting fair participants to options for year-round health care, and empowering fair participants with the tools necessary to take their health into their own hands. Since its start in 2000, Share the Health Fair’s mission has been to provide basic medical screenings and information on health care and healthy living for all members of the Winston-Salem community, especially those who may not otherwise have adequate access to these services. It is an entirely student-organized effort, providing a unique opportunity for WFUSM students to learn about community health and promote well-being within the community that has welcomed us as students pursue medical education. Share the Health Fair hosts hundreds of attendees per year and offers several integral and highly requested services including dental care, pap smears, and vision care. In 2025 it was staffed by > 200 volunteers and provided screening services and healthcare to >350 attendees. Additionally, this year we tackled food and hygiene insecurity, handing out thousands of dollars of hygiene products, shelf stable foods, and hot meals.
DEAC Clinic: The DEAC (Delivering Equal Access to Care) Clinic is a student run physician staffed free clinic whose mission is to provide high-quality, free healthcare to the underserved patients in our community while also creating a unique service oriented-learning experience for the students of Wake Forest. Since its inception in 2008, we have been providing primary care to uninsured patients in our community every Monday night. Through our clinic, we provide a great opportunity for our students to experience primary care firsthand while also performing a vital service to our community members. While we focus on primary care, our clinic also offers multiple other services to our patients in an effort to provide holistic care. First, we offer specialty nights approximately once every other month across six specialties including orthopedics, gastroenterology, neurology, pulmonology, cardiology, and dermatology. Through these specialty nights, we address gaps in the care of our patients that otherwise would not be able to be filled. We also offer two auxiliary clinics to for patients in our community; the DEAC Foot and Ankle Clinic and the DEAC Vision Clinic. The Foot and Ankle Clinic provides podiatric care and a free pair of shoes to unhoused patients in our community who desperately need it. The DEAC Vision Clinic provides free ophthalmologic care which includes free glasses and even surgery for patients who need it. Finally, through DEAC Outreach, we are able to go out into the community and screen patients for chronic diseases such as hypertension and diabetes while also increasing our visibility within the community.
In addition to these services, we also realize that providing primary care requires addressing not only our patients’ medical issues but also their social determinants of health. In order to achieve this goal, we have multiple programs aimed at closing these gaps. First, through our partnership with campus kitchen we are able to provide a meal and a produce bag for each patient who comes to our Monday night clinic. We are also currently working to expand this service for our Foot and Ankle and Vision Clinics. Recently, we have implanted a hygiene cart at our clinic stocked with soap, deodorant, toothbrushes, and many other essentials that patients are welcome to take when they come for their appointments. Lastly, we have also begun screening our patients for other needs that they may have such as transportation or help paying rent or utilities. We then use this information to refer them to local organizations that provide assistance in the particular area that they require it. Through addressing these social determinants of health, we strive to provide holistic primary care to our patients.
Programs Offered:
- Specialty Nights: The clinic hosts specialty nights across six different specialties, including Orthopedics, Neurology, Gastroenterology, Pulmonology, Cardiology, and Dermatology. These nights provide essential services to patients who otherwise would not have access to such care.
- Vision Clinic: This clinic offers complete, dilated eye exams and prescription glasses to patients. It also refers patients to Atrium Health Wake Forest Baptist Eye Center for further management of ocular conditions.
- Foot and Ankle Clinic: This clinic provides foot care to the homeless population, including foot exams, podiatrist visits, and distribution of foot care kits.
- Patient Navigator Program (PNP): This program connects patients with medical student volunteers who help them achieve their health goals through bi-weekly phone calls.
- Care Coordinator Role: Care Coordinators help bridge the gap between DEAC workflow and patient needs, connecting patients to healthcare access, specialty appointments, and community resources.
- Food Insecurity Project: In partnership with Campus Kitchen, this project provides meals to patients.
- Stopping Tobacco by Organizing Peers (STOP): This program offers smoking cessation therapy, including counseling, group sessions, and nicotine replacement therapy.
- Care Provided: The DEAC Clinic offers students an opportunity to experience first-hand a wide range of medical services, including primary care, specialty care, vision care, foot care, and smoking cessation therapy. It also provides essential medical supplies, such as prescription glasses, CPAP machines, oxygen tanks, and foot care kits.
Impact on Patients and the Community:
- Visits and Patients: From July to December 2025, the clinic had 125 total visits, serving 62 unique patients. Throughout the entire year, there were 229 visits and 87 unique patients.
- Volunteer Contributions: students volunteered 815 times, and preceptors volunteered 86 times during 2025.
- Specialty Nights: The clinic hosted 22 specialty nights, providing services to across 135 visits.
- Vision Clinic: The Vision Clinic served 43 patients, ordered 38 pairs of prescription glasses, and referred 18 patients for further management.
- Foot and Ankle Clinic: This clinic served an average of 33.8 patients each month, providing foot care and distributing foot care kits.
- Patient Navigator Program: The program currently has 12 enrolled patients and 16 student patient navigators.
- Food Insecurity Project: Campus Kitchen donated 96 meals to patients over 16 Mondays.
Key Outcomes: The DEAC Clinic has significantly improved access to healthcare for populations in Western North Carolina. The specialty nights and various clinics have provided essential medical services that patients would otherwise not have access to. The Patient Navigator Program and Care Coordinator Role have enhanced patient care coordination and support. The clinic’s outreach initiatives and public relations efforts have strengthened community engagement and awareness of its services.
Schweitzer Fellowship: The North Carolina Albert Schweitzer Fellowship is a prestigious, service-focused program that supports graduate students in implementing community-based health initiatives aimed at reducing health disparities and addressing the needs of underserved populations. Each year, Schweitzer Fellows design and carry out innovative, impactful projects in collaboration with local agencies, while also participating in interdisciplinary learning experiences that cultivate their leadership and professional development. For the 2025-2026 fellowship year, two new programs were launched under the Schweitzer Fellowship umbrella to address critical gaps in healthcare access and preventative services in North Carolina.
SEE: Screening Eyes and Education Program: The first initiative is the Screening Eyes and Education (SEE) Program, designed to address eye health disparities among underinsured and uninsured populations in the Winston-Salem area. The program’s primary objective is to provide free eye health screening events at Downtown Health Plaza (DHP) on a quarterly to monthly basis. In addition to screenings, the program offers referrals for follow-up care to those in need.
Participants at these events receive no-cost services that include basic eye examinations, referrals to free clinics, eye health education, and nutrition counseling aimed at reducing risk factors associated with eye disease.
Mobility Matters – Acute Care for the Elderly (ACE) Unit, Winston Salem & Charlotte: Mobility Matters is a student-led initiative at Wake Forest School of Medicine focused on improving the health and independence of hospitalized older adults at the Acute Care for the Elderly (ACE) Unit at Atrium Wake Forest. The program trains medical student volunteers to safely mobilize patients during their hospital stays; helping them sit, stand, and walk earlier, while also connecting them to community resources and mobility aids to support a safe transition home. The program addresses a critical and often overlooked problem: older adults spend over 90% of their hospital stay immobile, increasing their risk of deconditioning, falls, delirium, and readmission. By embedding mobility into routine care, the initiative aims to reduce these preventable complications and support patients in maintaining their independence after discharge.
Program Outcomes to Date:
- Served approximately 70 patients in the ACE Unit
- Recruited and trained 6 medical student volunteers
- Developed standardized training materials, patient surveys, and post-discharge follow-up protocols
- Expanded the program to Charlotte-notably of the patients mobilized, only one has been readmitted due to a fall; a notably low rate that speaks to both the safety approach and the impact of early mobilization on patient outcomes.
Selected Programs within the WFUSM Curriculum:
The “Wake Ready!” curriculum provides an individualized approach to prepare students towards their medical career. It advances WFUSM’s national reputation for graduating first-rate clinicians, educators and scholars. It provides students with flexibility to explore their interests and positions graduates for outstanding performance in the top residency training programs in the nation.
Clerkships: As part of the Wake Ready Curriculum, students complete a variety of community rotations/experiences between our two campuses (Winston-Salem and Charlotte) during their clerkships, with the opportunity to participate in electives in the post-clerkship curriculum. During the clerkship curriculum, all students complete an Ambulatory Internal Medicine (IM) clerkship and Family Medicine clerkship. Students also complete ambulatory components during their Pediatrics, Psychiatry, Neurology, and Obstetrics/Gynecology clerkships. A description of the dedicated community/ambulatory clerkships of Ambulatory IM and Family Medicine are included below.
Clerkship: Ambulatory Internal Medicine
Duration: 2 weeks on the Winston-Salem campus and comparable longitudinal clerkship on the Charlotte Campus
Description of Clerkship: The core clerkship in Ambulatory Internal Medicine focuses on the basic competencies of ambulatory internal medicine and management of chronic disease. Students spend time in various ambulatory settings which include continuity care clinics, complex care teams, and urgent care clinics. Students are expected to participate in the care of patients presenting to these clinics, including but not limited to conditions such as COPD, Diabetes, Hyperlipidemia, Hypertension, Obesity, Tobacco Use, Depression, and Joint Pain. Also, as part of the clerkship, students complete a Population Health Quality Improvement (PHQI) activity. In this project, they review the charts of ten patients they have cared for to identify gaps in preventive screenings and immunizations. Students then take active steps to close these health maintenance gaps by engaging directly with the patients identified through the PHQI process.
Participants in clerkship: All third year medical students on the Winston-Salem and Charlotte campuses (approx. 145 total)
Outcomes: Participation in care of patients with the above listed diagnoses/conditions and completion of the Population Health Quality Improvement project.
Clerkship: Family Medicine
Description of Clerkship: The Family Medicine clerkship is a 4 week clerkship on the Winston-Salem campus and Charlotte campus during the 2023-2024 academic year. The clerkship consists of students participating in patient care at the outpatient family medicine clinics in both Winston-Salem and Charlotte. Students are expected to participate in the care of patients presenting with back/neck pain, dysuria, headache, joint pain, rashes, asthma/COPD, depression, diabetes mellitus, hyperlipidemia, hypertension, obesity, respiratory illness, and tobacco use. Students also participate in adult and pediatric maintenance health exams and counseling on substance cessation.
Participants in clerkship: All third-year medical students on the Winston-Salem and Charlotte campuses (approx. 145 total)
Outcome: Participation in care of patients with above noted presentations, along with final exam in course (NBME exam).
Additionally, during the clerkship phase of the curriculum, students also complete the Health Equity thread/curriculum. This longitudinal curriculum encompasses a series of activities that focuses on health equity and the social determinants of health, such as housing, transportation, food insecurity, access to care, vulnerable patient populations, maternal-fetal health disparities as examples. Often, the experiences are partnered with a community organization in Winston-Salem and Charlotte that are working to address these disparities.
Longitudinal Health Equity Thread
Goals of Program:
- Understand the scope of health disparities in the United States.
- Identify ways to contribute to the reduction of health disparities as a practicing clinician.
- Demonstrate the knowledge and skills needed to improve the health of underserved populations.
- Explore activities with community partners that will foster an interest in careers working with underserved populations.
Number of participants: All third year medical students at both the Winston-Salem and Charlotte campuses (approx. 145 students)
Outcomes: Students engage with multiple community-based organizations and complete a variety of exercises throughout the curriculum that address health equity and the social determinants of health. Wake Forest medical students also have an opportunity to participate in a variety of fourth-year electives that offer robust clinical experiences in primary care. These electives provide exposure to outpatient and community-based practices across Family Medicine, Obstetrics and Gynecology, Pediatrics, and Psychiatry.
Electives that offer primary care-focused Family Medicine experiences include Rural Primary Care, Safety Net Healthcare: Bridging Gaps and Building Advocacy, and Urban Underserved Family Medicine. All Wake Forest University medical students on both the Winston-Salem and Charlotte campuses have the opportunity to participate in these electives during their fourth year.
The Rural Primary Care elective provides students with hands-on experience caring for full-spectrum Family Medicine patients, including adults, geriatrics, pediatrics, and newborns. Students rotate within rural primary care practices alongside interprofessional teams and engage in activities aimed at improving the health of the community. They gain experience in a variety of care delivery models, including virtual care, home visits, hospital care, and traditional office-based visits. Students may choose from three sites located in rural North Carolina counties.
Through NC AHEC Rural Health Teaching Hub funding, the Cabarrus Family Medicine Residency Program—part of Wake Forest University School of Medicine—has expanded opportunities for both medical students and APP learners to train in rural practice settings through a team-based teaching model. This initiative supports rural preceptors with stipends and provides learners with financial assistance for housing and mileage, reducing key barriers to rural rotations. As a result, engagement in rural training has grown significantly. Previously, rural experiences for fourth-year students were informal and student-directed, but in 2024, a formal fourth-year elective was established to intentionally place learners within these rural teaching hubs. Since its launch, participation and interest have continued to increase, strengthening the pipeline of trainees exposed to and considering careers in rural health.
The S_afety Net Healthcare: Bridging Gaps and Building Advocacy_ elective combines clinical experiences in Federally Qualified Health Centers (FQHCs) and Rural Health Clinics (RHCs) with interactive workshops, community partnerships, and didactic sessions. Students develop a deeper understanding of the rewards and challenges faced by safety net providers while building practical skills in advocacy and community engagement. This elective emphasizes healthcare systems serving Medicaid, uninsured, and underinsured populations, and focuses on advancing health equity and addressing social determinants of health. The course fosters a commitment to reducing health disparities and supporting vulnerable patient populations. The Urban Underserved Family Medicine elective immerses students in established neighborhood clinics and community settings, where they gain firsthand experience providing care to diverse, medically underserved populations. The course leverages community partnerships and local resources to demonstrate how family physicians address barriers to healthcare access and deliver culturally competent, patient-centered care. Students work alongside family physicians and interprofessional teams to provide comprehensive care, while also learning public health approaches such as Community-Oriented Primary Care (COPC). In addition, they are introduced to tools like geographic information systems (GIS) to analyze population health trends and better understand the unique needs of the communities they serve.
Appendix C
A Roadmap for a Statewide (and Nationwide) Approach to Training Primary Care Physicians Who Will Practice in Rural North Carolina
An AHEC Proposal to develop a Collaboration between NC Medical Schools
Objectives
- Improve the supply and distribution of physicians in needed specialties in rural communities and other communities with less access to resources to create a healthy North Carolina.
- Facilitate a path into medicine for students from rural and other underserved communities who might otherwise not have been able to envision themselves as future physicians.
- Develop and extend learning opportunities across the state of North Carolina through community-based learning and relationships.
Summary
Medical students will choose their specialty based on financial, personal, and professional goals. A medical student is more likely to choose to practice rural primary care if they are from a rural community, are trained in a rural community and are supported in practice once they locate in a rural community. A multi-pronged approach is needed to address this set of complex and important decision points. The different components of the approach are described in more detail below.
AHEC has been convening educational leaders of the two state medical schools to focus on 1) how to recruit more students who are likely to pursue careers in needed specialties, 2) how to train students in high quality rural primary care while in medical school and 3) how to create and support high functioning rural practices in which to teach students. The other components – residencies and post-training support in addition to scholarships, loan forgiveness and increased reimbursements - are also critically important and need to be addressed in a different manner. We are working together to develop a pilot Pathway to Primary Care that, once developed, could be extended to any interested North Carolina medical school and other health professional programs.
Critically Important Areas of Focus to Achieve Objectives
To reach these objectives, the program will:
- Recruit students into medical school who are more likely to pursue careers in needed specialties in rural and other underserved communities (Linkage Programs into Medical School)
- Train these students in high quality primary care while in medical school (Rural Tracks with Focused Curriculum)
- Creation and Support of high functioning primary care practices able to effectively teach (Select Teaching Practices)
- Invest in expanded and new rural residency programs. There are opportunities to leverage state and federal partnerships and create training programs in rural communities and resident naïve hospitals to increase the access to training opportunities where people are from and where they are needed for the future workforce.
- Help students match into appropriate residencies and support them during residency training (Facilitated Primary Care Residency Training)
- Provide further support and training after residency to optimize their successful entry into practice in rural and other underserved areas (Fellowship Training Programs)
- Provide financial support during training to allow learners to focus on their training and not be burdened by debt load that dissuades them from pursuing careers in primary care with a goal of entering practice without debt (Scholarships and Loan Forgiveness Programs)
- Continue to work at a national and state level to increase financial investments in primary care to allow for long-term sustainability of primary care practices (Increase Primary Care Reimbursement)
Figure 3. Pathway for Training Physicians to Serve Rural NC
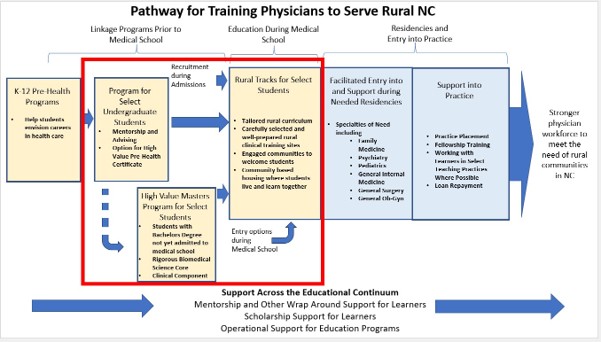
The diagram above describes the Pathway from K-12 through rural primary care practice. The red box focuses on the portion of the Pathway related to medical school selection, education and training.
Area of Focus #1: Linkage Programs from Undergraduate Training Programs and Post Baccalaureate Master’s Program
- Strengthen pre-health advising system at each of the 16 UNC System Schools to effectively prepare interested students for careers in medicine and other health care careers through shared resources (e.g. webinars, websites) and specific training of advisers. The focus is students who are likely to pursue careers in rural medicine.
- Develop a Pre-Health Certificate in participating UNC System Schools. The Certificate is developed in collaboration with the admissions committees of participating medical schools and holds high value in the admissions process. Focus on students who are likely to pursue careers in rural medicine.
- Collaborate with existing and evolving Master’s Program in the UNC System to offer a rigorous biomedical science core and an integrated clinical component for students with a Bachelor’s degree who have an interest in rural medicine and need additional preparation prior to applying to medical school. The value of the master’s Program is communicated to the admissions committees of participating medical schools and holds high value in the admissions process.
Key components of the program include 1) mentorship and 2) curriculum focusing on professional formation, clinical skills, and academic preparation.
Universities in the UNC System will be selected based on their interest in participating and their ability to recruit students who will likely pursue careers in rural and other underserved areas.
The educational collaborative convened by AHEC will further refine these programs.
Program participants who matriculate into medical school are guaranteed a place in the Rural Track described below and will learn in high performing Select Teaching Practices in rural communities.
Area of Focus #2: Focused Curriculum with Community Health Service Track/Training
This track would expand the total number of students engaged in rotations and experiences across rural and less resourced communities. It will also build a cohort of students who can support and grow with each other both in school and when practicing and will, hopefully, encourage more students to select rural primary care. In addition, having a specific and named rural track/training for students committed to rural practice will provide students additional leverage for residency placement through an LCME accredited track. Medical Schools participating in the collaboration will either have such a track already in existence or will develop such a track. Schools may choose to name their track differently. The components below are draft components of what such a track would include. Over the past year, the UNC SOM has incorporated many of these components in developing a Community Health Training Program. It was informed by the lessons learned from the FIRST Program (Fully Integrated Readiness for Service) and the Kenan Rural Scholars Program as well as the statewide work of the AHEC program. 24 first year medical students enrolled into the program in the Fall of 2025.
The educational collaborative convened by AHEC will further refine this area of focus.
Participating medical schools will work together to offer students an augmented rural and underserved curriculum. This will allow team formation among students who have shared commitment to education and engagement in rural and underserved communities across the state.
The track focuses on training medical students to become physicians who will serve rural and other underserved communities and will better prepare medical students and serve as a recruitment incentive for students considering careers in primary care.
Sample Program Components:
- Mentorship – Entering into Community Health Track, every student will be assigned a rural health preceptor. They will help students develop a statewide network of support that will provide important academic, professional, and social development.
- Curricular Enhancements – Students in the track will complete all core requirements of the respective medical school curricula, but in addition will learn skills essential to being a rural physician in NC such as enhanced procedural skills including advanced point of care ultrasound skills.
- Training in rural hospitals for a portion of required and elective inpatient experiences.
- Training in Select Teaching Practices for the majority of outpatient clinical experiences – Select Teaching Practices are essential to the success of this program and are currently underdeveloped at most medical schools. For this reason, Creation and Support of Select Teaching Practices is discussed as a separate area of focus.
Area of Focus #3: Creation and Support of Select Teaching Practices
Students will learn clinical medicine in teaching practices that are chosen based on the location of the practice in a rural or otherwise underserved setting, the quality of care delivered in the practice, and the high commitment to education. These practices will receive additional support and training to allow them to effectively train Track students.
The creation of high functioning primary care practices in which to teach learners (Select Teaching Practices) deserves further discussion. Developing these Select Teaching Practices is fundamental to ensuring a well-prepared primary care workforce for our future as these practices will provide learners with the skills and role modeling needed to succeed in primary care. Five such hubs have been funded to date by the NC Legislature and students are learning in those sites. Implementation of the teaching hubs is well underway and NC AHEC is at the early stage of evaluating this program.
Sample Components that make Select Teaching Practices different from currently existing community preceptors:
- Engaged Practices that provide high quality care. Select Teaching Practices are high functioning primary care offices that provide a broad range of services to patients and have an enthusiasm for passing on their knowledge to the next generation of primary care clinicians. Select Teaching Practices teach regularly so they can hone teaching skills and so that students integrate effectively into practice and directly contribute to the care of patients. Teachers in Select Teaching Practices participate in occasional events to help improve their teaching skills and help improve the curriculum. Select Teaching Practices are important members of the teaching team will have an important voice in how students are trained. The rural hubs funded by the General Assembly are required to have students from two or more professions (medical students and physician assistant or nurse practitioner student) more than half the time. They have also developed or plan to develop interprofessional practice and education.
- Select Teaching Practices are reimbursed at rates that allow them to teach effectively and remain financially viable. High performing practices face multiple pressures and increased reimbursement will allow them to compensate physicians and other staff to effectively teach students. The General Assembly funded hubs are supported by $150,000 per year.
- Select Teaching Practices teach learners from multiple health disciplines to allow for high quality interprofessional education that is needed to prepare an effective health workforce of the future.
- Students learning in these sites are incorporated into the rural communities in which the Select Teaching Practices are located. Housing is located in the communities to foster community integration and collaborative learning. Such immersive experiences are known to increase commitment to pursue careers in rural primary care. Adequate short-term housing continues to be a challenge in many communities.
- Students assigned to Select Teaching Practices intend to pursue careers in primary care. These students are carefully selected for their interest in primary care and will receive focused training in high quality primary care. Select Teaching Practices are thus able to teach a highly motivated group of students that share the practices enthusiasm for rural primary care.
- Students assigned to Select Teaching Practices make useful contributions to care. The same group of students are assigned to Select Teaching Practices over time so that they get to know the practice. This allows students to contribute to patient care in meaningful ways. The students are able to assist in value-based care, patient education, documentation, and other tasks.
Lessons being learned from these sites will be used to refine the current hubs and develop proposals to expand to other communities. The educational collaborative convened by AHEC will help in this process.
Figure 4. Summary Diagram of Focus Areas 1 -3 described above
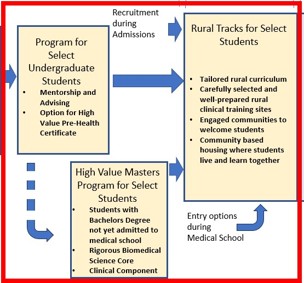
Additional Areas of Focus that are important but are not currently part of this collaborative:
Additional Area of Focus: Facilitated Primary Care Residency Training
Participating residencies will ensure that Track students continue to receive mentorship and support during residency.
The goal of this longitudinal approach is to train students in needed specialties to work in rural and underserved communities. Formal training often ends with residency. A minority of medical students from NC medical schools will practice primary care or psychiatry, and far fewer still will practice in rural and underserved areas.
Graduate Medical Education (GME) in NC has grown from 4 communities 50 years ago to 26 communities now. Most GME outside of academic health centers is in primary care. Training residents in the communities in rural and urban communities where people live and work is a proven strategy to increase provider supply and improve access to care. Additional community-based residencies to align with this Pathway are needed.
Students from the track will be encouraged to schedule guest rotations with aligned community-based residency programs. These students will be encouraged to consider these programs as ideal opportunities to train in the types of communities they want to live and work in and develop professional connections to those communities.
Additional Area of Focus: Fellowship Training Programs
Upon completion of residency, the program would support entry into practice with additional fellowship training. Fellowship training will provide enhanced clinical and business skills to succeed in rural practice. The fellowship will also provide teaching skills to grow the next generation of elite teaching practices.
MAHEC and UNC Office of Rural Initiatives have developed a rural fellowship program. Recently trained providers with employment in a rural community can have a portion of their professional time covered by the fellowship (10-20%) to allow the physician time to develop specific skills for rural practice as well as networking and rural leadership development. This fellowship has demonstrated early success and efforts will be made to expand it statewide. AHEC Practice Support can provide support to practices that employ recent graduates. Support includes assistance in areas such as practice management, quality improvement, electronic health record optimization, behavioral health integration, and workflow redesign. Ideally, these graduates could also practice in a Select Teaching Practice.
Additional Area of Focus: Financial Support and Reduction of Loan Burden
Loan burden on students graduating from medical school has increased dramatically over the past decade. The current average debt of graduating medical students nationally is now about $200,000. With continued wide disparities in salaries between specialties, large debt burden can influence student choice of specialties.
Programs to minimize financial pressures during training and reducing eventual total debt burden are an important part of ensuring an appropriate physician workforce in rural and other underserved communities. The goal of this program is to have participants enter practice with zero debt. Ideally, this program would align with the scholarship and loan repayment programs recently enacted by the General Assembly.
Additional Area of Focus: Increase Primary Care Reimbursement
Work at a national and statewide level to implement the recommendations of the National Academies of Science Engineering and Medicine to pay for primary care teams to care for people not doctors to deliver services. The report recommends that:
- Payers should evaluate and disseminate payment models based on the ability of those models to promote the delivery of high-quality primary care, not on achieving short-term cost savings.
- Payers using a fee-for-service (FFS) model should shift primary care payment toward hybrid (part FFS, part capitated) models and make them the default over time.
- The Centers for Medicare & Medicaid Services (CMS) should increase the overall portion of spending going to primary care.
- States should implement primary care payment reform by facilitating multi-payer collaboration and by increasing the overall portion of health care spending in their state going to primary care. Implementing high-quality primary care begins by committing to pay primary care more and differently because of its capacity to improve population health and health equity for all of society, not because it generates short term returns on investment for payers. High-quality primary care is a common good promoted by responsible public policy and supported by private-sector action.
Reducing student debt and increasing reimbursement are essential components as students weigh their personal and professional goals when choosing a medical specialty.
Selected References
- Implementing High Quality Primary Care: Rebuilding the Foundation of Health Care. The National Academies of Science, Engineering and Medicine 2021. https://www.nationalacademies.org/our-work/implementing-high-quality-primary-care
- Multiple Models exist on which this proposal is built. Links to some of these programs are provided below:
- Alabama College of Community Health Sciences: https://cchs.ua.edu/rural-programs/rmsp/#:~:text=The%20Rural%20Medical%20Scholars%20Program,where%20they%20are%20most%20needed
- Michigan State: https://msururalhealth.chm.msu.edu/programs/rural-physician-program.html
- U of Minnesota: https://med.umn.edu/md-students/individualized-pathways/rural-physician-associate-program-rpap
- NE Ohio Medical School: https://www.neomed.edu/medicine/admissions/paths/early-assurance/
- Eight Year Continuum. Brown Rhode Island. https://plme.med.brown.edu/
- JAMP with support from Texas Legislature: https://www.uta.edu/academics/schools-colleges/science/degree-programs/health-professions/special-programs-volunteering-research-opportunities/jamp
- WWAMI; Recruit students from rural communities and enroll them in Rural Track (TRUST). https://www.uwmedicine.org/school-of-medicine/md-program/wwami
References
-
NC DHHS Office of Rural Health. Safety Net Sites website. Accessed February 27, 2025. https://www.ncdhhs.gov/divisions/office-rural-health/safety-net-resources/safety-net-sites. ↩︎
-
Phillips WR, Park J, Topmiller M. Pathways to Primary Care: Charting Trajectories From Medical School Graduation Through Specialty Training. Health Affairs. 2025;44(5):580-588. https://doi.org/10.1377/hlthaff.2024.00893 ↩︎ ↩︎
-
Hawes EM, Lombardi B, Adhikari M, Galloway E, McDougal L, Biszewski M, Fraher EP. “Physician Training In Rural And Health Center Settings More Than Doubled, 2008–24.” Health Affairs. 2025;44(5):572-579. https://doi.org/10.1377/hlthaff.2024.01297 ↩︎ ↩︎
-
Patterson DG, Shipman SA, Pollack SW, Andrilla CHA, Schmitz D, Evans DV, Peterson LE, Longenecker R. “Growing a rural family physician workforce: The contributions of rural background and rural place of residency training.” Health Services Research. 2024;59(1):e14168. https://doi.org/10.1111/1475-6773.14168 ↩︎ ↩︎
-
Chen C, Chen F, Mullan F. “Teaching Health Centers: A New Paradigm in Graduate Medical Education.” Academic Medicine. 2012;87(12):1752-1756. https://doi.org/10.1097/ACM.0b013e3182720f4d ↩︎ ↩︎
-
Galloway E, Lombardi B, Fraher EP. The Workforce Outcomes of Physicians Completing Residency Training in North Carolina in 2017, 2018, and 2019. UNC Cecil G. Sheps Center for Health Services Research; June 30, 2025. https://nchealthworkforce.unc.edu/projects/medical-education-and-training-outcomes/gme-tracking-2025/ ↩︎ ↩︎
-
Iglehart J. The challenging quest to improve rural health care. NEJM, 2018. 378(5):473-479. https://www.nejm.org/doi/full/10.1056/NEJMhpr1707176 ↩︎
-
Paralkar N, LaVine N, Ryan S, Conigliaro R, Ehrlich J, Khan A, Block L. Career Plans of Internal Medicine Residents From 2019 to 2021. JAMA Intern Med. 2023 Oct 1;183(10):1166-1167. http://doi.org/10.1001/jamainternmed.2023.2873. Erratum in: JAMA Intern Med. 2024 Mar 1;184(3):336 ↩︎
-
National Resident Matching Program (NRMP). Main Residency Match Results and Data, 2023–2026. Washington, DC: NRMP. Available at: https://www.nrmp.org/about/news/2026/03/nrmp-releases-results-of-the-2026-main-residency-match-for-more-than-38000-future-residents/ ↩︎
-
Stanford Socioeconomic Position Indices (SEPI). Reproducible Area Deprivation Index (ReADI). Stanford University. https://sepi.stanford.edu/. ↩︎
-
Gladish N, Phillips RL, Rehkopf DH. Estimation of Mortality via the Neighborhood Atlas and Reproducible Area Deprivation Indices. JAMA Network Open. 2026;9(1):e2546800. http://doi.org/10.1001/jamanetworkopen.2025.46800 ↩︎